Standards & Evaluations Committee and the Tropical and Geographical Neurology Specialty Group

By Wolfgang Grisold

Wolfgang Grisold

In this issue, we want to introduce the World Federation of Neurology (WFN) Standards & Evaluations Committee, chaired by Prof. László Vécsei, and the specialty group on Tropical and Geographical Neurology, chaired by Dr. Chandrashekhar Meshram.

All WFN committees are listed on the WFN website, as well as the members of the committees and specialty groups. We are thankful, and acknowledge the work of the committee and the specialty group members. In these articles, we will just mention the chair as the representative for the group.

The WFN Standards & Evaluations Committee

This committee is chaired by Prof. László Vécsei from Szeged, Hungary. Prof. Vécsei is the head of Neuroscience Research Group in the Department of Neurology, Faculty of Medicine at the Albert Szent-Györgyi Clinical Center, University of Szeged, Hungary. Prof. Vécsei has much experience in working in neurological international societies and is presently the secretary-general of the Danub Group. (http://danubeneurology.eu). The committee has several experienced members who are actively involved in the review and decision process.

Prof. László Vécsei

Prof. László Vécsei

The important task of the WFN Standards & Evaluations Committee is to evaluate applications from international or national neurological congresses and any other scientific meetings in neurosciences in classical forms and as virtual meetings, for WFN accreditation that apply according to its guidelines as noted on the WFN application form, which can be reached on the WFN website: https://www.wfneurology.org/meetings-endorsement.

The task of this WFN activity is to keep and improve the standards of the neurological scientific meetings applying for WFN endorsement. This is done according to a structured guideline. Information on the required ethical issues and limitations with regard to relations with the pharmaceutical and other industries are to be found in the application form.

Once a completed application is received, it is reviewed by the committee, and applicants are notified of the decision within two weeks of their application.

A meeting endorsed by the WFN qualifies to use the WFN logo, it is announced on the WFN website and WFN newsletter and after the meeting, a brief summary can be published on the website or in World Neurology.

In addition to meetings, this committee reviews and accredits neurology related guidelines or books or other enduring material which requests WFN accreditation. Depending on its content, it may be reviewed together with the Education Committee, or with the aid of experts or the speciality groups.

The Tropical and Geographical Neurology Specialty Group

Dr. Chandrashekhar Meshram, MD, DM

Dr. Chandrashekhar Meshram, MD, DM

This Specialty Group is chaired by Dr. Chandrashekhar Meshram, MD, DM( PGI Chandigarh), India, who is supported by an active membership. He is a consultant neurologist and director of the Brain and Mind Institute in Nagpur, India, and past-president of the Indian Academy of Neurology (2013-14). Prof. Meshram has been active in many agendas for the WFN in the past years.

The specialty group on tropical neurology introduced a timely webinar series in 2020 (see below) on neurological infectious diseases, with an excellent scientific content, impeccable technical support, and has successfully sparked the interest on neuroinfections worldwide.

The Tropical Neurology Specialty Group is the oldest WFN research group established in 1961. The Specialty Group (formerly “Applied Research Group”) was formed with the mission to foster research collaboration in aspects of neurological disorders prevalent in the tropics and to disseminate knowledge at international and regional levels. The specialty group holds regular congresses (INTROPICON-https://worldneurologyonline.com/article/tropical-neurology-intropicon-2018/), and publishes a special issue on Tropical Neurology in the Journal of Neurological Sciences

Jointly with the Forum for Indian Neurology Education (FINE) and Indian Academy of Neurology, a neuroinfection webinar series was introduced and endorsed by the WFN.

These sessions usually consist of a main lecture and three case presentations.

In the first series, talks were given on neurocysticercosis, cerebral malaria, zika and other arbovirus infections, neurobrucelloisis, encephalitis, cryptococcal meningitis, fungal meningitis as well as the general approach to neurologic infections, among other topics.

During series 2, talks on 12 more topics were organized and given. A weblink allows continued viewing of these sessions: https://us02web.zoom.us/j/87248087732.

All of These Activities Are Free.

This timely webinar series in 2020 on infectious diseases was designed at the right time and helped to introduce new technologies, enabling the scientific community to communicate and interact during the harsh and still unpredictable times of COVID. •
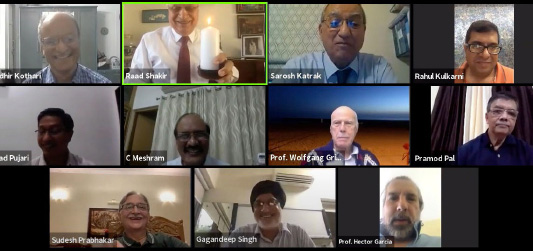
Screenshot capture of the inaugural meeting of the 2020 FINE/WFN Neuroinfection Webinar series in 2020.

Screenshot capture of the inaugural meeting of the 2020 FINE/WFN Neuroinfection Webinar series in 2020.
National Brain Week 2020 in India

By Chandrashekahr Meshram, JMK Murthy, Nirmal Surya, U Meenakshisundaram and Gagandeep Singh

Examples of print media coverage from National Brain Week 2020 in India.

Examples of print media coverage from National Brain Week 2020 in India.

Taking inspiration from the World Federation of Neurology (WFN), the Indian Academy of Neurology has been organizing public education and awareness programs on brain health and brain diseases during National Brain Week for the last seven years with Chandrashekhar Meshram as the convener. The activity is held with the academy’s Foundation Day, which is Dec. 16.

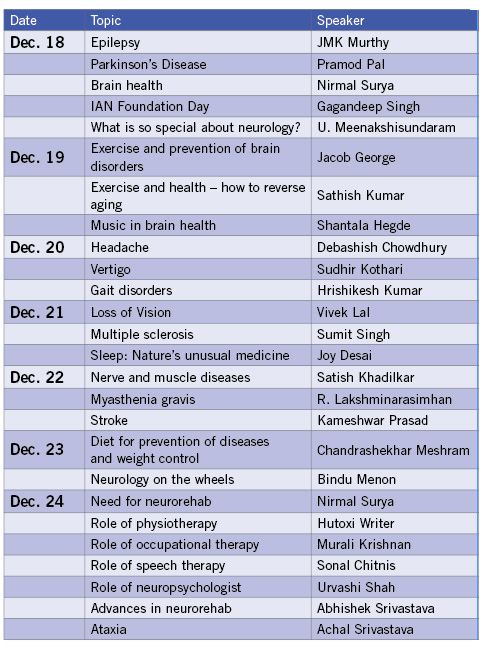
National Brain Week was organized as a virtual event this year on the background of the ongoing coronavirus pandemic. Neurologists and experts across the country joined the week-long celebration. The sessions were conducted online daily from Dec. 18-24.

This year’s theme was “My Health My Responsibility.” The emphasis was on preventive aspects of the neurological diseases. Dr. Meshram planned the program for the week and released the press note.

Program for National Brain Week India held in December 2020.

Program for National Brain Week India held in December 2020.

Past President of the Academy and philanthropist Padmashree Dr. Ashok Panagariya inaugurated the event and addressed the audience on Dec. 18.

After the sessions’ concluding function was held, IAN President Dr. JMK Murthy, President-Elect Dr. Nirmal Surya, Secretary Dr. U. Meenakshisundaram, Past-Secretary Dr. Gagandeep Singh, Convener Dr. Chandrashekhar Meshram and Dr. Partha Ray expressed their views about the extremely successful event. Important information regarding the diseases and their prevention was conveyed in the best possible way. Difficult topics were made simple by speakers for understanding by the general public.

The faculty came from different regions and states of the country. After the talks, the audience got the opportunity to interact with the experts during question-and-answer sessions. During the week, the IAN 3000k Challenge was also organized; 58 neurologists ran for 3109 kms during the week and set the example for the society.

There was an overwhelming response to the event. Print media actively participated in the campaign. (5 Figures) The academy has decided to undertake public education and awareness activities more frequently throughout the year during 2021. •

Inspiring People in Neurosciences

By Dr. Chandrashekhar Meshram

After the hugely successful educational neuro-infection series with 16 fascinating sessions, the World Federation of Neurology’s Tropical and Geographical Neurology Specialty Group in collaboration with the Indian Academy of Neurology is organizing a new series. “Inspiring People in Neurosciences” explore legends who have done great work in the field of neurosciences.

The idea is to ignite young minds to do outstanding work in the field of their choice.

This monthly series will be held 6:30 p.m.-8 p.m. Indian Standard Time (1 p.m.-2:30 p.m. GMT) on the first Saturday of each month.

The series, which started Feb. 6, 2021, was inaugurated by WFN Secretary General Prof. Wolfgang Grisold. WFN President Prof. William Carroll sent a video message that was played for the audience.

The first session’s inspirational person was Prof. David Molyneux, emeritus professor at Liverpool School of Tropical Medicine and University of Liverpool in the U.K. The session was chaired by former WFN President Prof. Raad Shakir. Prof. Molyneux gave a talk on neglected tropical diseases. After his talk, Prof. Peter Hotez, Prof. Juerg Utzinger, Prof. Simon Bush, and Prof. Alan Fenwick made important comments.

Registration is free. Link for the registration: https://forms.gle/BX3xyKcztAWzLGyu6

Link to join the program: https://us02web.zoom.us/j/81137122193 A password is not required. •

Upcoming Sessions

  • March 6: Louis Caplan will talk about Prof. C. Miller Fisher
  • April 3: Kailash Bhatia will talk about Prof. David Marsden
  • May: Angela Vincent will talk about John Newsom-Davis
  • June 5: Allan Ropper will talk about Prof. Raymond Adams,
  • July 3: Prof. Bhim Sen Singhal will talk about Prof. Noshir Wadia

Report From Morocco Trainees in 2020

By Dr. Olivier Kapto and Dr. Ratsitohara Santatra Razafindrasata

We are Dr. Olivier Kapto, Cameroonian, neurologist at Ouagadougou, Burkina Faso, and Dr. Ratsitohara Santatra Razafindrasata, Malagasy, neurologist at Antananarivo, Madagascar. We are both interested in clinical neurophysiology and are happy to have benefited from the World Federation of Neurology’s (WFN’s) one-year fellowship at the neurophysiology unit of Ibn Sina Teaching School in Rabat, Morocco. We worked under the supervision of Drs. Reda Ouazzani (head of unit) and El Alaoui Mustapha Faris from January 2020 to December 2021.

The neurophysiology unit has two electroneuromyography rooms under the supervision of Drs. Nazha Birouk, Leila Errguig and Bouchra Kably, one evoked potential room supervised by Dr. Bouchra Kably, one video-EEG room and one standard EEG room under the supervision of Drs. Reda Ouazzani, Leila Errguig and Fatiha Lahjouji.

We were assigned since the beginning in these different units from 9 a.m. to 3 p.m. every Monday through Friday. Many learning activities are usual in the department: EEG staff with review of clinical cases, interpretation and literature review every Wednesday morning; general staff to discuss EEG-video cases for epilepsy surgery and electroneuromyography review of weekly cases about clinical, technical, and interpretation aspects every Thursday afternoon.

In the EEG unit, we learned the importance of patient history, electrode installation, and results interpretation. We assisted with visual and sensory evoked potentials. The EMG unit has been the most prolific. We started as observers in anatomical landmarks and technical realization. We gradually learned to do it ourselves, and at the end, we are able to perform and interpret an EMG exam. We have seen many cases: carpal tunnel syndrome, polyneuropathies, traumatic injuries, polyradiculoneuropathies, brachial plexus injuries, lumbar plexus injuries, myogenic syndrome, neuromuscular junction syndrome, amyotrophic lateral sclerosis, and facial palsies, among many others. The key point for us is the importance of clinical examination in the EMG test. We had the chance to attend neuromuscular and epilepsy consultations.

Our biggest difficulty was the lockdown, but we continued online learning with Dr. Birouk about the clinical and technical aspects of neuromuscular diseases. We took part in many scientific meetings online.

We are grateful to the WFN for this opportunity. We hope it will help us to continue in neurophysiological specialization. We thank the Moroccan authorities for administrative facilitations. We say a big thanks to Drs. Ouazzani, Birouk and their team. Our journey with them was so nice and instructive.

Many thanks, Dr. El Alaoui for your availability and care of us. Our biggest regret is not having the possibility to visit more of Morocco with the lockdown. We think we will come again.

It’s a pleasure for us to wish happy New Year 2021 with further expansion of neurology. •

Notice of Elections for 2021

This October, at the Annual General Meeting (AGM) of the Council of Delegates (COD), elections will be held for the following positions:


President. To take office Jan. 1, 2022 (position vacated by Prof. William Carroll).

First Vice President. To take office Jan. 1, 2022 (position vacated by Prof. Ryuji Kaji).

One Elected Trustee. To take office from date of election in October 2021 (position vacated by Prof. Alla Guekht who is eligible for re-election).

The names of candidates to be considered for nomination can be submitted together with written confirmation of their willingness to stand for election, a brief curriculum vitae (a single type-written page) and written support for their nomination from their national societies. These should reach the WFN London Secretariat office by Monday, April 12.

The Nominating Committee will scrutinize all submissions received and compile an official list six months before the date of the election.

Candidates for the positions of president and first vice president will be required to provide a statement of their goals and objectives for the WFN if elected, which will be published in World Neurology. They will also be required to present a short statement by video prior to the election at a date to be advised. Videos will be available for viewing on the website before the election process begins. This date will also be advised.

Please note that following the closing date, additional nominations can be submitted up to 30 days before the election process by five or more member societies acting jointly.

As in 2020, elections will be conducted electronically in time for the announcement of the successful candidates at the AGM. •

Good News at the End of 2020

The WHO calls for global action plan to combat epilepsy and other neurologic disorders

By William Carroll

As we reach the end of a very trying year with COVID-19 still rampant, I have two pieces of good news, in some respects, as good as the imminent arrival of the vaccines.

The first is a momentous decision by the WHO and the second is an important and rewarding development for the WFN. Both point us all in the same direction.

William Carroll, MD

The decision by the World Health Assembly (WHA) on Nov. 12, 2020, to adopt Resolution WHA73.10 is a landmark event. Although the WFN has been closely involved with neurological activities within, and related to, the WHO, the call for the development of global action plans to combat epilepsy and (importantly) neurological disorders, is a first. It comes courtesy of a sustained effort by the ILAE (led recently by Prof. Sam Wiebe) and International Bureau for Epilepsy (IBE) to convince the WHO that epilepsy is a common disease, causing considerable effect upon people, their neurological health, their cognitive function, societal burden, and individual stigmatization for want of the ready availability of anticonvulsant medication.

William Carroll, MDIt also occurred through the recognition of certain key member states that saw the synergies between the dilemma of epilepsy and those suffering from it, with a number of other important neurological processes. The resulting WHA73.10 Resolution was carried unanimously by members of the 74th Executive Board and thence the 73rd World Health Assembly. In Clause (PP2) of WHA73, it is clear that the authors and the supporting member states recognized a need to address all neurological disorders. The clause specifically mentions epilepsy, headache disorders, neurodevelopmental, neurodegenerative, neuroinfectious/neuroimmunological, cerebrovascular diseases including stroke, and traumatic brain and spinal cord disorders. There is scarcely a single neurological disorder not encompassed by this regulation. (See below.)

The regulation seeks to develop a comprehensive intersectoral approach to addressing all neurological disorders in line with the third pillar of the U.N. Sustainable Development Goals.

For the first time, neurological disorders are being overtly recognized for the threat they pose to all societies and health jurisdictions. We need look no further than the most recent Global Burden of Disease Study, which demonstrated neurological non-communicable disorders to be the leading cause of disability and the second leading cause of death. To have the WHO acknowledge the need for global action plans to address this burden will provide enormous assistance to those at risk of neurological disorders and those attempting to combat them.

The WFN was proud to lend its support to the ILAE and IBE at the WHA71 (May 2018) “Side Event for Global Action on Epilepsy” and a statement calling for a new report on the implementation of Resolution WHA68.20 to be prepared for discussion at the WHA74 meeting in 2021.

Photo of WHA 73 from the WHO website.]

At the 144th Executive Board Meeting in January/February 2019, the WFN posted a statement asking the EB not to defer consideration on further actions to address the global burden of epilepsy and its health and social implications at the country level. Again, in May 2019, we joined with the ILAE and IBE to support this initiative in a further Side Event, urging member states to implement a coordinated action against epilepsy through the establishment of:

  1. national Health Care Plans for epilepsy management to overcome inequalities and inequities in health, social, and other related services
  2. initiatives to promote public awareness of an education about epilepsy, and to reduce the misconceptions, stigmatization and discrimination against people with epilepsy
  3. actions to prevent causes of epilepsy
  4. greater investment in epilepsy research and increased research capacity.

The WFN also posted a statement on the Prevention and Control of Non-Communicable Diseases (Agenda item 11.8) highlighting the need to:

  1. elucidate treatments to prevent and/or modify stroke, migraine, and Alzheimer’s Disease and other dementias
  2. the disparity between high and low sociodemographic index nations and the resultant unequal burden on resources
  3. that the WFN was uniquely placed as the only global neurological organization with an almost identical matching regional and national reach.

The statement pointed to the WFN’s geographical advantage in advocacy partnership being bolstered by its relationship with associated disease topic organizations of the Global Neurological Alliance, such as the World Stroke Organization, Alzheimer’s Disease International, Parkinson’s Disease and Movement Disorders Society, the International League Against Epilepsy, and Multiple Sclerosis International Federation.

At the 146th Executive Board meeting in February 2020, the WFN supported the draft decision on the 2019 Global Report “Epilepsy as a Public Health Imperative” proposed by the Russian Federation and co-sponsored by China and Guyana. The WFN statement also requested the WHO director-general to expand the scope of the report EB146/12 to be presented at the 73rd WHA with an additional consideration of “Synergies in Addressing the Burden of Epilepsy and Other Neurological Disorders” and among other calls “to encourage member states and related non-state actors to contribute to discussions” on the “draft resolution on epilepsy and other neurological disorders” based on the report mentioned in paragraph 2 to be presented for consideration by the 73rd WHA.

The leadership demonstrated by the WHO in the adoption of WHA73.10 will be of inestimable benefit in the energization of all those faced with combating neurological disorders, particularly non-communicable neurological disorders and their devastating effect on individuals and societies. For those so engaged to know that the WHO, through its member states, will be encouraging, advocating, and leading the intersectoral struggle will be heartened.

There will be many non-state actors, such as the WFN, that will be similarly buoyed. To address these challenges in the manner outlined in the WHA73.10 Resolution will also require the development and implementation of plans to overcome many barriers, which have contributed to the inequities of access most keenly felt by less well-resourced jurisdictions. The leadership of the WHO will be pivotal in maintaining the momentum required.

Finally, this most welcome event sits closely with the WFN Needs Registry. This registry was conceived to provide a complementary balance to the data supplied by WHO member states. Member states are by and large national governments. The WFN Needs Registry is the product of WFN member societies, which are in turn composed of neurologists and allied neurological colleagues on whom people with neurological disease depend for prevention, diagnosis, and treatment. The data collected by the Needs Registry offers opportunities to advocate for the redirection of resources as well as additional resources where possible and to do so collectively with member societies and jurisdictions sharing common challenges.

Given the position of the WFN and its relationship with the Global Neurology Alliance and the World Health Organization, it is likely to be able to contribute considerably to the attainment of useful outcomes in line with WHA73.10. In this regard, the WFN is planning to discuss in 2021 with each of its regional organizations ways in which these processes might be advanced.

I wish you your families and colleagues a safe and joyous time through the festive season and a better New Year for all. •

The 73rd World Health Assembly Resolution WHA73.10

(PP1) Recognizing that epilepsy and other neurological disorders are the leading cause of disability-adjusted life years and the second leading cause of death worldwide, and that epilepsy and other neurological disorders disproportionately impact people living in low- and middle-income countries;1

(PP2) Noting that neurological disorders are conditions of the central and peripheral nervous system that include epilepsy, headache disorders, neurodegenerative disorders, cerebrovascular diseases including stroke, neuroinfectious/neuroimmunological disorders, neurodevelopmental disorders and traumatic brain and spinal cord injuries;2

(PP3) Noting with concern that the risk of premature death in people with epilepsy is three times higher than in the general population and that, over the past 30 years, the absolute number of deaths due to neurological disorders has increased by 39%;3

(PP4) Acknowledging, as outlined in the WHO/ International League Against Epilepsy/International Bureau for Epilepsy Global Report on Epilepsy (2019), that epilepsy is one of the most common neurological disorders globally affecting an estimated 50 million people worldwide across all ages with increased rates in the young and the old…

(OP1) URGES Member States:1

(OP 1.1) To provide the appropriate support to WHO to develop the Intersectoral Global Action Plan on Epilepsy and Other Neurological Disorders referenced in paragraph 3.1;

(OP2) CALLS UPON all relevant stakeholders:

(OP2.1) To provide appropriate support to WHO and partners to develop the Intersectoral Global Action Plan on Epilepsy and Other Neurological Disorders referenced in paragraph 3.1;

(OP3) REQUESTS the Director-General:

(OP3.1) To develop, in consultation with Member States, and in full collaboration with United Nations organizations and relevant non-State actors, a 10-year Intersectoral Global Action Plan on Epilepsy and Other Neurological Disorders in support of universal health coverage to address the current significant gaps in promotion of physical and mental health, and prevention, early detection, care, treatment and rehabilitation, as well as social, economic, educational and inclusion needs of persons and families living with epilepsy and other neurological disorders, and the ongoing need for research to improve prevention, early detection, treatment, care and rehabilitation, including treatment options with the potential to cure epilepsy and other neurological disorders;

(OP3.2) To include in the Intersectoral Global Action Plan ambitious, but achievable, global targets on reducing preventable cases of, and avoidable deaths, resulting from epilepsy and other neurological disorders, strengthening service coverage and access to essential medicines, improving surveillance and critical research and addressing discrimination and stigma;

(OP3.3) To submit to the 150th Executive Board, a draft Intersectoral Global Action Plan for consideration by Member States, as well as to report on the progress achieved in implementing this resolution, with an intention to submit the plan to Member States for endorsement during the 75th World Health Assembly. •

Palliative Care for Patients With Stroke

By Wolfgang Grisold, Claire J. Creutzfeldt, Gillian Mead, and Fergus N. Doubal

During the World Stroke Organization (WSO)-European Stroke Organization (ESO) Congress (https://eso-wso-conference.org), a teaching course on palliative care issues in patients with stroke was offered. There were four speakers: Wolfgang Grisold (Austria), Claire J. Creutzfeldt (U.S.), Gillian Mead (U.K.), and Fergus N. Doubal (U.K.). They presented four lectures.

This initiative deserves merit, as despite much progress in palliative care in many aspects of neurology, there is considerable scope for improving palliative care in stroke. Stroke is the most frequent neurological disease globally and the leading cause of disability adjusted life-years and deaths due to neurological diseases. Therefore, such an initiative is important, and, as this teaching course showed, has many facets to be discussed.

Wolfgang Grisold (Austria)

Wolfgang Grisold

W. Grisold gave an outline on the present international guidelines on palliative care in stroke. Guidelines are elaborate and define the need and the role. In addition, there is also a U.K. patient guide that is helpful. Most of the guidelines are aimed at the acute and subacute setting of stroke, and further work needs to be done for the long trajectory of stroke survivors.

Attention also needs to be given to individuals with disturbed consciousness, cognitive impairment, and speech disorders, who often can not actively participate in the process of decision-making.

From the conceptual and cultural point of view, it has to be acknowledged that the concept of palliative care is based on the patient autonomy, which is culturally perceived differently.

Claire J. Creutzfeld (U.S.)

Claire J. Creutzfeld

The issue of integrating palliative care and serious illness communication into high quality stroke care was addressed by C.J. Creutzfeldt. The different disease trajectories were discussed and compared with those of other illnesses often considered for palliative care, such as cancer. Building a partnership with the patient and his or her family, communicating transparently and discussing hope with both realism and compassion are key skills for stroke providers. Dr. Creutzfeldt gave a strong testimony of the need for palliative care in stroke with the goal of improving communication, decision-making, quality of life, and quality of end of life for patients with stroke and their families.

Gillian Mead (U.K.)

Gillian Mead

Gillian Mead emphasized the role of families and also the importance of communication. An important issue is what the individual expectancy for patients with severe stroke is, and if this would change at different time points during their disease, as survival often ensues with severe disability.

Reference to the study of Kendall et al, 2018, was made, which posed the question of outcomes, experiences, and palliative care in stroke.

One result was that palliative care still has the connotation of withdrawal, or withholding, and “dual“ narratives should be avoided. The loss of the former self of the patient is an issue for the patient and for carers. Guiding through the moral maze in discussions with the family is important for providing emotional support and dignity.

Fergus Doubal (U.K.)

Fergus Doubal

Sudden death is common following stroke and can be due to several causes: immediate pressure effects from a large stroke causing brain edema, concurrent severe disease, often cardiac, infectious, and other medical complications, and also due to treatment withdrawal.  In young adults, stroke is the fourth most common cause of sudden death after cardiac causes, pulmonary embolism, and infection.

When stroke causes sudden death, especially in younger patients, there is a preponderance of intracerebral hemorrhages compared to ischemic stroke. When stroke causes death within 24-48 hours, the rate of intracerebral hemorrhage is higher, but as time progresses ischemic stroke become more prevalent as a cause of death.

When death is sudden (within days), this can be challenging for patients, families, and health care professionals who often need to work together to make important yet time-critical shared decisions quickly. During this process, it is important to base decisions on the patient’s values and what they would consider to be an acceptable outcome with families acting as proxies should the patient not retain capacity to participate. Often death may not be considered the worst outcome compared to survival in a highly dependent state.


References for Further Reading:

Holloway RG et al. Palliative and End-of-Life Care in Stroke. Stroke 2014; Volume 45, Issue 6,1887-1916.

https://www.stroke.org.uk/resources/national-clinical-guideline-stroke-patient-version


Claire J. Creutzfeldt, et al.  Symptomatic and Palliative Care for Stroke Survivors. J Gen Intern Med. 2012 Jul; 27(7): 853–860.


Marylin Kendall, et al. Outcomes, experiences and palliative care in major stroke: a multicentre, mixed-method, longitudinal study. CMAJ. 2018 Mar 5;190(9):E238-E246. doi: 10.1503/cmaj.170604.


Frederik Nybye Ågesen, et al. Sudden unexpected death caused by stroke: A nationwide study among children and young adults in Denmark Int J Stroke  2018 Apr;13(3):285-291. doi: 10.1177/1747493017724625. Epub 2017 Aug 1.


Wolfgand Grisold is Secretary-General of the WFN.


Claire J. Creutzfeldt is associate professor of neurology at the University of Washington – Harborview Medical Center in Seattle, Washington.


Gillian Mead is chair of Stroke and Elderly Care Medicine at the Center for Clinical Brain Sciences, University of Edinburgh.


Fergus Doubal is the Stroke Association Garfield Weston Foundation Clinical Senior Lecturer,


NHS Scotland Research Fellow at the Center for Clinical Brain Sciences, University of Edinburgh.

Letter from the editors

By Steven L. Lewis, MD, Editor,
and Walter Struhal, MD, Co-Editor

Steven L. Lewis, MD, Walter Struhal, MD

We would like to welcome you to the December 2020 issue of World Neurology, the final issue of this remarkable year. This issue begins with the exciting news from WFN President William Carroll about the recent decision by the World Health Assembly on Nov. 12, 2020, to adopt Resolution WHA73.10, calling for a global action plan to combat epilepsy and other neurologic disorders.

With regard to the WFN as a source of high-level global neurologic education, this issue features the article by Nobutaka Arai, head of the Laboratory of Neuropathology at Tokyo Metropolitan Institute of Medical Science, whose website teaching neuroanatomic and neuropathologic concepts is available free to all neurologists worldwide and available as a link in the article and on the WFN website.

In addition, Prof. Riadh Gouider provides an exciting update and the successful statistics from the recent WFN/AFAN e-learning Day, which took place in October and was attended by hundreds of neurologists worldwide.

Wolfgang Grisold, Claire J. Creutzfeldt, Gillian Mead, and Fergus N. Doubal provide their report on the recent teaching course they organized for the World Stroke Organization and European Stroke Organization on palliative care for patients with stroke, as an emerging and necessary development in the care of stroke patients.

This issue also offers an inspiring article, reprinted with permission from the Royal Society (https://www.rcplondon.ac.uk/news/doctor-can-journey-bedwin-boy-eastern-sudan-professor-neurology) describing the journey of Prof. Osheik Seidi from Sudan.

In this issue’s History column, Prof. Peter Koehler provides us with additional insights into the background and interests of the anatomist Sylvius, of aqueduct and lateral fissure fame.

In his column on WFN Committees and Specialty Groups, WFN Secretary-General Wolfgang Grisold updates us on the activities of the e-Communications Committee and the Aphasia, Dementia, and Cognitive Disorders Specialty Group of the WFN.

This issue also features a nicely illustrated and thoughtful report from the recent participant in the WFN department visit at St. Olav’s Hospital in Norway, an opportunity created through the generosity of and wonderful planning from the Norwegian Neurological Association.

Finally, the issue concludes with a heartfelt obituary of Dr. Juan Rafael Santoni Mendoza, a father of Dominican neurology.

We wish you all a happy and healthy 2021 and look forward to your reports and suggestions for articles in the new year! •

Essential Brain Anatomy & Neuropathology (EBA&N)

Nobutaka Arai

The Tokyo Metropolitan Institute of Medical Science (TMiMS) began its operations in April 2011 as a new institute integrating the formerly independently operated three institutes; the Tokyo Metropolitan Institute for Neuroscience, Tokyo Metropolitan Institute of Psychiatry, and Tokyo Metropolitan Institute of Medical Science. The Laboratory of Neuropathology (LONP) in TMiMS manages the neuropathological assets of both the former institutes and the brand new one.

LONP has created a digital archive of normal and pathological images of the human central nervous system, and operates Essential Brain Anatomy & Neuropathology (EBA&N) that can be viewed at: https://pathologycenter.jp/english/en_index.html

This system was awarded the Tokyo Metropolitan Association of Medical Welfare and Health Excellence Award in 2014 and the Tokyo Metropolitan Government Staff Award (Governor’s Award) in 2016. In 2017, this website was certified as an intellectual property  of TMiMS.

EBA&N consists of various whole slide images (Cellular Neuropathology, Disease Cytopathology, Normal Histopathology, Muscle Diseases), in addition to brain cutting videos and many photographs. It is very easy to understand because the commentary is written directly on the images and videos, not as footnotes.

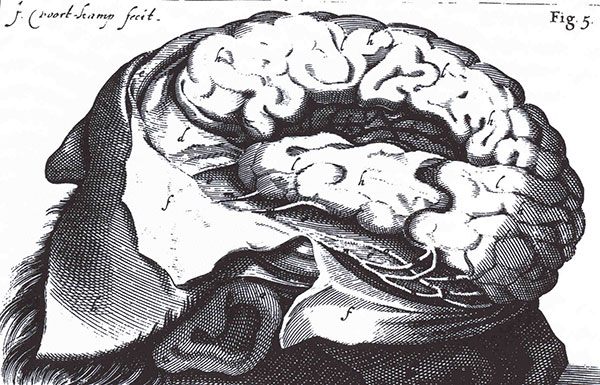
We are pleased to issue an individual account to those who wish to view it, so please apply by using the application form in the sample room on the EBA&N site. Registration is completely free. No special browsing software is required. We welcome anyone interested in neuroanatomy and neuropathology. •

Sylvius and “The Quack”

Masterpieces at a Leyden Home

By Peter J. Koehler

When reading the name Sylvius, most neurologists will think of neuroanatomic structures like the aqueduct and the lateral fissure of the hemispheres. Descendant from a Protestant family from northern France (the city of Cambrai that at the time was situated in the southern Netherlands), Franciscus dele Boë (1614-1672), also known as Sylvius, was born in the German town of Hanau, east of Frankfurt-am-Main.

Sylvius by Frans van Mieris I (1665, oil on
panel, 18,8×14,2 cm, New York, private
collection; see also The Leiden Collection
FM-104).

He studied medicine in Sedan and Leyden, made a peregrination to southern German universities and defended a thesis at the university of Basel, Switzerland (1637). He graduated a second time the following year at Leyden university.

He became famous for his anatomy lessons, at the time including physiology. He demonstrated the circulation of the blood as published by William Harvey (1578-1657) a few decades previously (De motu cordis, 1628).

“Many students, and certainly not the worst ones, attended his courses, so that it seemed as if only he could understand and explain anatomy.” Among his students was Danish Thomas Bartholinus (1616-1680), son of the famous anatomist Caspar (1585-1629). Thomas’s notes of Sylvius’s course of the early 1640s was included in his father’s Institutiones anatomicae (1641 edition). Caspar Bartholinus wrote “we cannot pass by the very accurate anatomist D. Franciscus Sylvius; from his noble mind and ingenuity we take the admirable new structure of the brain.”

Following a period of practicing general medical in Amsterdam (1641-1658), where he lived at the Keizersgracht [canal], and during which he enjoyed chemistry and anatomy in his leisure time, he returned to Leyden to become professor of medicine. He gave bedside teaching in the nearby Caeciliahospital and studied the pathological changes at autopsy.

Fissure of Sylvius

Fissura Sylvii.

He attracted many foreign students, including Danish Niels Stensen (“Steno”; 1638-1688), who wrote that Sylvius’s method of brain dissection was a combination of the ancient Galenic approach and the more recent method of Costanzo Varolio (1543-1575).

The latter cut the brain from its base to above, thereby improving the visualization of structures at the base, including the cranial nerves and the pons (Varolius). Another pupil, Gabriel Ypelaer, defended a thesis under Sylvius’s supervision, in which he presented a description of the lateral fissure (1660). Sylvius published it three years later in his own Disputationem medicarum decas.

In 1774, the Swiss Albrecht von Haller (1708-1777) emphasized that this was probably the first description of the fissure. Sylvius’s name became also associated with the aqueduct, although many refer to the homonymous teacher of Andreas Vesalius (1514-1564), Paris anatomist Jacobus Sylvius (1478-1555).

Probably the structure had already been observed by others before Jacobus Sylvius, although there is discussion on whether they really saw the small canal. The Leyden Sylvius, however, described the “canalis vel aquae-ductus” between the converging “roots of the spinal cord” and the corpora quadrigemina below “our bridge” (Disputationem (1663; chapter 21).

With respect to physiology, Sylvius rejected the classical qualities and humors, retaining the concept of animal spirits that were used in the brain and sent to the muscles through the nerves. He adhered to a kind of chemical humoral pathology that became known as iatrochemistry, in which effervescense, a vehement reaction between acid and alkaline secretions occur, for instance, in the right ventricle of the heart or the duodenum.

Collecting Masterpieces

Sylvius and his wife / “The music lesson”
by Frans van Mieris I (1672, oil on
panel, 41×31 cm, courtesy Staatliche
Kunstsammlungen Dresden – Gemäldegalerie
Alte Meister, Dresden, inv. no. 1743).

Sylvius’s first wife, Anna de Ligne, whom he married in 1649, died the year before he moved back to Leyden. Their two children also died at a young age. Arriving in Leyden, he bought a nice house at Rapenburg (on a canal) no. 31, not far from the university building. He had it converted (for 10.500 guilders) into a distinguished home with dining room and salon.

Other houses at the Rapenburg were owned by upper-class Leiden citizens, including city official, merchants, and like Sylvius, university professors. An inventory of his house in 1673, half a year after his death, shows that he had been the owner not only of a considerable library, comprising hundreds of medical, chemical, and religious books, but also one of the largest painting collections of the city.

It seems that at the time he was a patron for contemporary painters, including Experiens Sillemans (1611-1652/3; six paintings) and Simon Luttichuys (1610-1661; six) from Amsterdam, and Gerrit Dou (11) and Frans van Mieris I (7) from Leiden. Among the latter painter’s works, Sylvius owned “The music lesson” with portraits of Sylvius and his second wife Magdalena L. Schletzer, whom he had married in 1666. During the plague of 1669, Sylvius became severely ill, but survived. However, his young wife (21 years old) died, even before Van Mieris finished the painting. It was hanging in Sylvius’s front room. For Van Mieris, Sylvius was “zynen Mecenas” [his Maecenas]. Dutch writer and painter Arnold Houbraken (1660-1719) wrote: “Professor Silvius, welke laatste dikwerf verzogt, dat al wat hy maakte voor hem mogt wezen” [Professor Sylvius, the latter who often asked that all what he made might be for him] (Houbraken, 1721, p. 3).

Next to the painting with his second wife, Van Mieris painted another portrait of Sylvius (1665, see above, he inscribed the age of the person 52, which should have been 50 or 51).

Furthermore, Sylvius owned works by Roelant Savery (1576-1639), Paulus Potter (1625-1654), and Philips Wouwerman (1619-1668), in particular animal scenes. Imagine living in such a kind of art gallery! A reconstruction of his home showed that he had 22 paintings in his dining room (including the five senses by Jan Miense Molenaer), 34 in his large salon, 26 in a side chamber, 16 in the upper back chamber, and 42 (including Van Dyck’s portrait of King Charles of England) in the master bedroom that was arranged as a kind of Kunstkammer.

Apparently, he did not collect everything from his surroundings, as is demonstrated by the fact that he did not have any of the moralizing genre pieces by Jan Steen (1626-1679) or landscapes of Jan van Goyen (1596-1656).

The Quack and (Brain)Stones

Sylvius’s house in Leyden at Rapenburg 31.

Since Jheronimus Bosch’s painting “Cutting the stone,” similar scenes have been depicted in paintings and engravings during the 16th and 17th century (see World Neurology 2017, January, pp. 6-7). Adriaen Brouwer’s (c.1605-1638) “Quacksalver,” now possessed by the Kunsthalle in Karlsruhe), was hanging in Sylvius’s entry room. Although it is not a representation of the actual procedure of “cutting the stone,” stones are depicted hanging on pieces of red string on the quack’s banner, in a way that can observed in several other paintings. It would indicate examples of stones that the quack had removed in the past from the heads of other patients. Even a knife has been attached to the banner.

The place of action is a market square, where a quack, who has relatively short legs, with long hair, a beard, and moustache, is standing on a partly sawed off or buried barrel. He is wearing a red hat with feathers, a yellow coat with blue stripes, and brown trousers. These clothes remind of the Italian comedy (commedia dell’arte), which was sometimes applied by painters. A dagger is attached to his belt. He seems to be looking at the viewer.

In his left hand, he has a small pot and with the index finger of the right hand he probably takes some ointment. Around the table in front of him, we see adult people, probably peasants listening and looking to the objects on the table. There are also some children. The one with the red beret with white feather and pink coat may be doing some mischief. The woman in brown blouse and white bonnet behind the table, laughing to the quack possibly took the plug from the bottle with the blue fluid, or is she emptying a small pot? To the right-hand side, a woman in pink coat with white bonnet and apron, is sitting on a low bench. A man in front of her seems to be explaining what is happening; he is pointing to the quack.

Two other persons, one with a red cap and the other a black beret, behind that man are discussing the scene. A man, leaning on the windowsill of the opened window above, and a woman behind him, are also listening. A number of objects are displayed on the table, including a small bottle with a plug, a spatula – it may be pointing in an intended direction –  and a bowl with a triturator. A big knife is hanging from the edge of the table.

At the background to the left, we see a farmer’s house and a church (and some persons, one of whom is obeying nature’s call near the tree) and to the right façades of six houses in a row. Deception of the credulous peasants seems to be the main subject of this scene.

If the viewer would still have doubts, the painter added, on the upper right corner of the banner, some letters: “JAN CERNAKEL.” This is a reference to Bruegel’s “Witch of Mallegem,” where it is spelled with a “k” instead of “c.” The German world “Karnickel” has several meanings, including rascal or bellwether.

The Pineal Gland and Brain Stones

“Der Quacksalber” [Quacksalver] by Adriaen Brouwer that once belonged to Sylvius.
(c. 1630, oil on panel, 45,2×61,8 cm, courtesy Staatliche Kunsthalle, Karsruhe, inv. no.1897).

Although the artists of the paintings and engravings that directly or indirectly refer to “cutting the stone” had moralistic or satirical intentions, rather than showing actual practices, it is funny to see that Sylvius at least owned one such painting. This is particularly interesting as he lived in a time, in which the pineal gland, by some, including René Descartes (1596-1650), Henricus Regius (1598-1679), and Louis de la Forge (1632-1666), was believed to be the organ in which the soul is localized.

The finding of calcifications, stones, in this organ led to several speculations. Some reasoned that these findings could never be compatible with the idea of localization of the soul in the pineal gland. Others, who had found such stones in persons with behavioral disorders (including a woman who committed infanticide), believed rather that it proved that the cause was in that organ. By its calcification, the physiological flow of humors in that area was believed to be prohibited (see World Neurology 2017, January, pp. 6-7).

In these discussions, the name of Sylvius (and English physician/anatomist Thomas Wharton [1614-1673]) was often found as opponents to the idea of attributing such a function to the pineal gland. The town physician of Nijmegen, subsequently professor of medicine and anatomy in Utrecht (1649), IJsbrand van Diemerbroeck (1609-1674), published a new edition of his Anatome Corporis Humane (1679; first edition 1672), in which he gave a description of the anatomy and position of the pineal gland, mentioning “arena & calculi” [sand and calcification] that occupied half the volume of the gland, with a reference to Sylvius, who indeed referred to the pineal gland in his Disputationes Medicarem IV (De Spirituum Animalium in Cerebro, Cerebelloque Confectione, per Nervous Distributione, atque Usu Vario). He was much in doubt about its function.

“Know Thyself”

This ancient Greek aphorism is one of the Delphic maxims depicted on a column of the Temple of Apollo. Smith (1999) believed that Sylvius’s painting collection “emphasized the importance of self-knowledge and the effort to achieve moderation in all things, like the numerous fruit and flower still lifes in his collection, which alluded to the ephemeral nature of human existence and the vanity of the things of the world, the message of neostoicism.”

Brouwer’s “Quacksalver” would also fit in this idea of admonition to temperance and several of the themes, also used in the literary arts of the period, including self-knowledge and “insight in the deceptive essence of the world.” It would be recognizable in Sylvius’s inaugural address, when he became professor in Leyden (1658). The painting in Sylvius’s collection gives evidence of his sense of humor as well as the perception of Van Mieris’s and Brouwer’s work among the public. •


FURTHER READING:


Baumann ED (1949). François dele Boe Sylvius. Leiden, Brill


Beukers H (2000). The Sylvian Fissure. In: Koehler PJ, Bruyn GW, Pearce JMS (eds). Neurological Eponyms. New York, Oxford University Press, pp. 51-5.


Houbraken A (1721/1976). De groote schouburgh der Nederlantsche konstschilders en schilderessen. Part III Amsterdam, Israël (see also http://www.dbnl.org/tekst/houb005groo01_01/colofon.php accessed October 1st, 2020).


Smith PH (1999). Science and Taste: Painting, Passions, and the New Philosophy in Seventeenth-Century Leiden. Isis 90 :421-461.