Practical Neurology in Moshi, Tanzania Initiative Aims to Train 200 Neurologists

By William P. Howlett, Marieke Dekker, and Sarah Urasa (KCMC)

Sarah Urasa

Marieke Dekker

William P. Howlett

In August 2015, the African Academy of Neurology (AfAN) was formed in Dakar, Senegal, and became the final regional member of the World Federation of Neurology (WFN). This membership is proving to be an important stimulus to neurology education and training in Africa.

A subsequent meeting of AfAN and regional members of the WFN, which took place at the World Congress of Neurology in November 2015 in Santiago, Chile, adopted a resolution to promote the training of 200 neurologists in Africa within the following 10 years.

Since then, in order to achieve this goal, a number of initiatives have taken place in Africa. One such initiative involves the East African Development Bank (EADB), an organization that currently includes four countries: Kenya, Rwanda, Tanzania, and Uganda. It involves funding a Medical Training and Fellowship (METAF) program, which is designed to support the neglected fields of neurology and oncology in East Africa.

The neurology program includes support for one- to two-year training fellowships in the U.K. for African neurology trainees and support for local training in neurology within East Africa.

Partnership

Group photo of course trainees, lecturers, and organizers.

The METAF program is planned in collaboration with local organizing partners and involves teaching hospitals and universities in East Africa and the Royal College of Physicians London (RCP) supported by representatives from the Association of British Neurologists (ABN) and managed by the British Council. Postgraduate doctors either training in internal medicine or pediatrics, or those recently graduated, are their target audience. The aim is to increase knowledge and awareness of neurology in Africa and to promote training in neurology, ranging from primary care to specialist neurologists.

To facilitate the implementation of METAF locally, adjacent countries—Tanzania/Kenya and Uganda/Rwanda—were paired into two groups with a series of two five-day courses planned per year, alternating between the host countries within each group. The setup was planned to continue for four years. Members of the teaching faculty for each course are chosen from the two host countries, with visiting lecturers from
the U.K.

The first series of these courses took place in September 2016 in Nairobi, Kenya, and Kampala, Uganda. A total of 34 trainees participated. The third course took place April 3-7 in Moshi in Northern Tanzania. It was attended by 20 trainees.

Practical Neurology Theme

The venue in Moshi was a local hotel with conference facilities. The theme of the Moshi course was “Practical Neurology,” with a comprehensive but practical review of the main neurological disorders experienced in Africa occurring in all ages. It also included a hands-on neurological examination. The course started and finished with a short pre- and post-training assessment. The covered topics ranged from infections— including HIV—to epilepsy, stroke, paraplegia, neuropathy, movement disorders, dementia, head injury, cerebral palsy, and genetic diseases. Interspersed between formal lectures were teaching video sessions and case presentations by the participants.

The course highlighted some important aspects for future neurology training in Africa. First, it is a practical example of a global AfAN/WFN initiative, which is funded from within Africa, supporting sustainability in the longer term. Second, it has resulted in North/South collaboration with neurologists/lecturers from within Africa and the U.K. coming together for the first time, all with the aim of teaching and training neurology in Africa. Third, the importance of participatory teaching methodology was underlined by the shared interest and excitement shown by the trainees, in particular with their case presentations and group discussions.

Ophthalmoscopy Exams
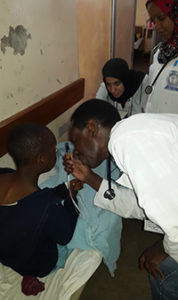
Trainee using an Arclight ophthalmoscope in the workplace.

An example of instant success was the provision of an affordable, handy, lightweight, easily rechargeable Arclight Ophthalmoscope free to everyone in the course, including teachers. This was introduced by David Nicholl, ABN honorary secretary. The candidates in the course were instructed on how to use the Arclight. The effect was palpably electric as they started to learn a practical skill and realized they could carry out funduscopic examinations upon returning to their workplaces across Tanzania.   

The course is just one of a number of ongoing initiatives aimed at developing neurology training in Africa. In the past five years, the Eastern African region has seen some significant developments, with adult and pediatric neurologists from the East African Community (EAC) countries of Burundi, Kenya, Rwanda, Tanzania, and Uganda joining forces professionally. The aim is to facilitate specialist neurology training for EAC doctors within Africa to make the region less dependent on external training facilities. This was supported by grants-in-aid from the WFN.

Tanzania has a population of 53 million and only seven practicing neurologists, and has huge unmet needs in neurology. One author (Dr. Howlett) has worked at Kilimanjaro Christian Medical Center (KCMC) in Northern Tanzania for over 30 years. He has experienced the start of neurology teaching/training of assistant medical officers followed by undergraduates, later postgraduates, and the training of one specialist in neurology. The same changes are happening all over Africa today. The historical post-colonial gap in neurology teaching/training and skills in Africa is well known; this neurology teaching course is another small step toward closing that gap. 

The authors are with the Kilimanjaro Christian Medical Center.
Eponymous Women in Neurology

By Peter J. Koehler

The term eponym is derived from the Greek words epi- “sur” and onima “name.” It is hardly possible to imagine daily life without eponyms, although we are not always aware of using them. Just think of diesel engine, pasteurized milk, degrees Fahrenheit or Celsius, to name a few. Eponyms are found in nearly all sciences, including mathematics, astronomy, physics, chemistry, geography, paleontology, and botany (to mention a few: Pythagoras, Gödel, Fourier analysis, Avogadro).

The use of eponyms is not new. Carl Linnaeus (1707-1778) used them in botany. Other eponyms became verbs (galvanize, faradize) or units (watt, ampère, ohm, joule). The French “préfet” (prefect) of the Seine department Eugène-René Poubelle made the use of garbage cans obligatory, hence the French word “poubelle” for garbage can.

And what about the grenadier in Napoleon’s army, Nicolas Chauvin, who made propaganda for Napoleon following his return from the Isle of Elba in 1815 (chauvinism!)? A Dutch author estimated the number of eponyms in everyday language at 2,500-3,000. The Eponyms Dictionary Index features approximately 20,000 eponyms, including scientific eponyms.2 

The choice of eponyms may tell something about the scientific evolution of the subject. Many eponyms in natural sciences, for instance, refer to persons from the 17th to 19th centuries, and the Scientific Revolution is supposed to have begun in the 17th century. As the scientific method in medicine was introduced in the mid-1800s, most medical eponyms find their origin after that period. Another interesting phenomenon to point to is that whereas 19th century eponyms are often single names, those from the late 19th and 20th century mainly consist of several names.2

Sources for Eponyms

Medical eponyms are derived from various sources. They are not only named after the discoverer of a disease or microbe who is honored (Borrelia Burgdorferi, Pick disease, Alzheimer’s). Sources also include mythical figures (Ondine’s curse, Oedipus complex), fairy tales (Alice-in-Wonderland syndrome), literature (Pickwick syndrome, Ophelia complex), artists (Brueghel syndrome), location (Lyme disease, Glasgow coma scale), and famous patients (Lou Gehrig).

An important source for finding the meaning of medical eponyms is www.whonamedit.com. The author, the Norwegian Ole Daniel Enersen, had the ambition to “present a complete survey of all medical phenomena named for a person,” with a short biography of that person.

Advocates and Adversaries

The use of eponyms is not generally accepted. There are adversaries and advocates. London neurologist William Gowers (1845-1915) wrote that “this system of nomenclature is full of inconvenience, increasing the difficulties of the student, and leading to frequent mistakes in scientific writings,”  but he could not prohibit the use of his name in several eponyms4. 

In his monograph on reflexes, Robert Wartenberg wrote that following the discovery by Joseph Babinski of the extensor plantar reflex, Wartenberg wrote about a plethora of discovered reflexes.

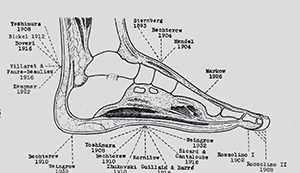
In his monograph on reflexes, Robert Wartenberg (1886-1956) wrote that following the discovery by Joseph Babinski (1857-1932) of the extensor plantar reflex (1896), a plethora of reflexes was discovered. The discoverers probably hoped to see their names immortalized. (See Figure 1.)5, p.93

The mania to associate eponyms to reflexes and phenomena was particularly endemic in Europe. Wartenberg was in favor of descriptive terms. However, descriptive terms also have disadvantages, for instance, when the understanding of phenomena or diseases change. Interestingly, he could not prevent the usage of his name for eponyms (e.g., Wartenberg sign for pyramidal involvement of the upper extremity).

A pro-con discussion on the use of eponyms was conducted some years ago in the British Medical Journal.6  The authors, who stated that the use of eponyms should be abandoned, provided several reasons, mostly quoting a short selection of rare, disputable eponyms. Of course, they were right proposing the deletion of eponyms connected with Nazi medicine. Larry Zeidman and colleagues have done research in this area during the past 10 years.7  The arguments that some eponyms may bring about confusion or do not refer to the original discoverer is often heard and probably true. The person writing in favor of eponyms provided more general arguments, including the opinion that the eponym “brings color to medicine,” “provides a convenient shorthand,” and are “embedded in medical traditions and culture in our history.” She expected eponyms would stay, despite the objections of some. Probably the shorthand and reference to the historical person are the most important arguments provided in favor of the use of eponyms.8

The Practical Use of Eponyms

Although done 20 years ago, a survey on neurological eponyms under Dutch neurologists (1997) provided interesting results. With 30 percent of the addressed members responding, a positive correlation was found between age of the responders and the knowledge of eponyms. The best-known eponyms were found in the category “tests and maneuvers.” Many of the responding neurologists and residents did not prefer descriptive terms above eponyms.9

In another paper on neurological eponyms, the author mentioned the confusion that may arise when it is not clear whether the eponym refers to a syndrome or a disease. Moreover, there is an evolution of some of the eponyms, as our understanding of disease processes expands.10 There is even an eponym about the doubts of the origin: Stigler’s law of eponymy states that “no scientific discovery is named after its original discover.”11

At least from a historical perspective, there is still interest in eponyms. Entering the term  “eponym” in PubMed and limiting the search to “history of medicine” provides 1,034 hits. Adding “neurology” results in 121 hits. And how is the use of eponyms in textbooks? The index of a neurological textbook, Adams and Victor’s Principles of Neurology, counted 370 eponyms.12  Another example, Merritt’s Neurology, did not yield much less.13

Eponymous Women in Neurology

Many eponyms concern men. Even if the name refers to a woman, not everyone will realize this. In April 2017, Dr. Stephen Reich, current chair of the History Section of the American Academy of Neurology, organized a history course in which eight eponymous women in neurology were presented. In the following section, I will summarize them.

Augusta Dejerine Klumpke and her husband.

Dejerine-Klumpe Syndrome / Augusta Dejerine-Klumpke

Born in San Francisco, Augusta Dejerine-Klumpke moved to Paris, where she studied medicine, and, not without difficulties, she became the first female intern of the Paris hospitals. She married Jules-Joseph Dejerine in 1888. She described the work by which she was eponymized in 1885 in the Revue de Médecine.14  It is about lower trunk brachial plexopathy with hand weakness. It is commonly associated with oculopupillary phenomena (Horner’s syndrome). It is also referred to as Klumpke’s paralysis. (The paper was presented by Jennifer McKinney.)

Roussy-Lévy Syndrome / Gabrielle Lévy

Gabrielle Lévy

Born in Paris, where she studied medicine, Gabrielle Lévy became a pupil of Pierre Marie. She published on many subjects, the most important being post-encephalitic syndromes, which was also the subject of her 1922 thesis, and neuro-oncology, a subject she worked on when employed at the Paul-Brousse hospital that became an oncology center.

The eponym refers to a familial disease with gait problems, areflexia, and clubfoot (dystasie aréflexive héréditaire), today known to be caused either by a mutation in the PMP22 gene or the MPZ gene (as in the original family).15  Lévy died at age 48 from the disease that she had studied: a brain tumor or a post-encephalitic syndrome? (The paper was presented by Peter J. Koehler.)

Louis-Bar Syndrome (ataxia telangiectasia)/ Denise Louis-Bar

Denise Louis-Bar (originally Bar, she married civil engineer F. Louis) published (in French) a case of this multisystem disease (ataxia, ocular-cutaneous telangiectasias, and immune deficiency) at age 27 (1941).16  Born in Liège, Belgium, she studied medicine in Brussels and trained under Ludo van Bogaert, with whom she studied the first case in Antwerp. Boder and Sedgwick published on eight children from five families in recognizing the hereditary character (1958).17  Louis-Bar later worked at the internal medicine department in Liège and was known there as “la rousse medical” (the medical red-haired). (The paper was presented by Elisabeth A. Coon.)

Dix-Hallpike Maneuver / Margaret Dix

Margaret Ruth Dix

Margaret Dix (1902-1991) received her MD in 1957, after she had ended her career as a surgeon (she became a fellow of the Royal College of Surgeons in 1943), following an eye injury during the bombing of England in World War II. She became a neuro-otologist and trained with otologist Charles Skinner Hallpike. They worked at the otological research unit of the National Hospital for Neurology and Neurosurgery in London. Dix wrote many papers on several subjects, including the two classic papers on benign paroxysmal positional vertigo and the eponymous maneuver18,19. (The paper was presented by Douglas J. Lanska.)

Canavan Disease / Myrtelle May Canavan

Born in 1879 near St. Johns, Michigan, Myrtelle May Moore received her MD from the Women’s Medical College of Pennsylvania and married physician James Francis Canavan. She became interested in neuropathology, and from 1920 until her retirement in 1945, she worked as associate professor of neuropathology at Boston University and curator of the Warren Anatomical Museum at Harvard Medical School. She described the disease to which her name became attached in 1931,20  and it is now known to be an autosomal recessive neurodegenerative disease caused by a mutation in the ASPA gene resulting in aspartoacylase deficiency. Canavan died from Parkinson’s disease in 1953. (The paper was presented by Lenora Lehwald.)

Hurler Syndrome / Gertrud Hurler

Gertrud Hurler was born in 1889 in Rastenburg, Prussia, and went to medical school in Munich. She trained as a pediatrician under Meinhard von Pfaundler. She was given the cases of two brothers with dysmorphic features to study and describe. In addition, the children had developmental delays and clouded corneas. She recognized the hypotonia, cognitive impairment, short stature, macrocephaly, scaphocephaly, delayed anterior fontanelle closure, course facial features with prominent facial hair as well as the hepatoplenomegaly. Hurler published her paper in 1919.21  Despite a subsequent paper on the subject in 1920 by Von Pfaundler,22  the disease remained attached to her name. She was probably not aware of the publication by Charles Hunter, working in Winnipeg, Canada, who described two brothers without corneal clouding. When serving in Europe during World War I, he gave a presentation at the Royal Society of Medicine in London: “A rare disease in two brothers.”23  Frederick Parkes Weber (1863-1962), who was present at the meeting, concurred with the diagnosis of “gargoylism.” (The paper was presented by Margie Ream.)

Frey’s Syndrome / Lucja Frey

Lucja Frey

Following injury of the auriculotemporal nerve (for example, by parotid gland surgery; gunshot injury in the case of Frey’s patient), inappropriate regeneration may result in gustatory sweating (Frey’s syndrome). Lucja Frey was born in 1889 in Lvov, Poland. She attended medical school in the same city and following graduation, she worked under Kazimierz Orzechowski. She presented on the syndrome of the auriculotemporal nerve in Warsaw (1923) and published on it in a Polish as well as a French (Revue Neurologique) journal. 24 She published a large number of papers on various subjects. During the German occupation, she worked at the Lvov Ghetto Polyclinic and was killed in 1942. (The paper was presented by Stephen G. Reich.)

The Mary Walker Effect / Mary Broadfoot Walker

The Mary Walker effect is a curious observation presented in 1938 during a meeting of the Royal Society of Medicine.25  In myasthenic ptosis, the drooping of the eyelid can be reversed by prostigmin. When the effect of the prostigmin is wearing off, circulation in the arms is cut off by inflation of cuffs (to 200 mm Hg). Exercise of the forearms in this situation does not increase the ptosis. However, 1.5 minutes after the release of the cuffs, the ptosis increases and 2 minutes after the release general muscle weakness increases. Mary Walker believed that myasthenic muscles released a curarizing agent during activity, which passed into the bloodstream and blocked neuromuscular transmission elsewhere. Although her speculative idea was not correct, it stimulated the search for a circulating factor. She was the first to clearly demonstrate that strength temporarily improved in patients with myasthenia gravis when they were given physostigmine or neostigmine and published on this in 1934.26  The pertinent film clip may be found at www.youtube.com/watch?v=uRoRsmvkhTI.

Born in 1888 in Wigtown, Scotland, Mary Walker received a bachelor’s of medicine and bachelor’s of surgery degree from Glasgow and Edinburgh Medical College for Women in 1913. She became a member of the Royal College of Physicians in 1932 and received her MD from the University of Edinburg in 1935. She worked as a salaried Poor Law Service medical assistant at the Greenwich Union Infirmary/St. Alfege’s Hospital from 1920 to 1936 and several other hospitals after that. She died in 1974. (The paper was presented by Christopher J. Boes.)

Peter J. Koehler is based in Heerlen, Netherlands. More history is provided at his website at www.neurohistory.nl.

References

  1. This paper is based upon the Introduction of the 2008 AAN History Course “Eponyms in Neurology” (by PJK) and the 2017 AAN History Course “Eponymous Women in Neurology”.
  2. Arts NJM, Koehler PJ, Bruyn GW. Inleiding [Introduction]. Het neurologisch onderzoek in eponymen [The neurological examination in eponyms]. Nijmegen, Arts & Boeve, 1995, pp.1-10.
  3. Gowers WR. The diagnosis of diseases of the spinal cord. London, Churchill, 1880.
  4. Toodayan N, Boes CJ. The eponymous legacy of Sir William Richard Gowers (1845-1915):
    A revealing letter. J Hist Neurosci 2017;26:169-192.
  5. Wartenberg R. The examination of reflexes. A simplification. Chicago, The Yearbook Publisher, 1945.
  6. Woywodt A, Matteson E, Whitworth JA. Should eponyms be abandoned? BMJ 2007;335:424-5.
  7. Kondziella D, Zeidman LA. What’s in a Name? Neurological Eponyms of the Nazi Era. Front Neurol Neurosci. 2016;38:184-200.
  8. Koehler PJ, Bruyn GW, Pearce JMS. Neurological Eponyms. New York, Oxford University Press, 2000, p.v-vi.
  9. Franke L, Koehler PJ, Bruyn GW. The use of and familiarity with neurological eponyms at the close of the 20th century by Dutch neurologists. An inventory Clin Neurol Neuro¬surg 1997;99:91-8.
  10. Okun MS. Neurological eponyms – Who gets the credit? J Hist Neurosci 2003;12:91-103.
  11. Stigler SM. Stigler’s law of eponymy. In: Gieryn TF, ed. Science and social structure: a festschrift for Robert K. Merton. New York, NY Academy of Sciences, 1980.
  12. Ropper AH and Brown RH. Adams and Victor’s Principles of neurology (8th ed.) New York, McGraw-Hill, 2005
  13. Rowland LP (ed). Merritt’s Neurology (11th ed.). Philadelphia, Lippincott, Williams & Wilkins, 2005.
  14. Dejerine-Klumpke A.. Contribution à l’étude des paralysies radiculaires du plexus brachial. Paralysies radiculaires totales. Paralysies radiculaires inférieures. De la participation des filets sympathiques oculo-pupillaires dans ces paralysies. Revue de Médecine 1885, 5: 591-616, 739-90.
  15. Roussy G, Lévy G. Sept cas d’une maladie familiale particulière: troubles de la marche, pieds bots, et aréfléxie tendineuse généralisée, avec, accessoirement, légère maladresse des mains. Rev Neurol (Paris). 1926;33:427-50. 
  16. Louis-Bar D. Sur un syndrome progressif cormprenant des télangiectasies capillaires cutanées et conjonctivales symétriques, à disposition naevoïde et des troubles cérébelleux. Confin Neurol 1941;4: 32-42.
  17. Boder E, Sedgwick RP. Ataxia-telangiectasia; a familial syndrome of progressive cerebellar ataxia, oculocutaneous telangiectasia and frequent pulmonary infection. Pediatrics 1958;21: 526-554.
  18. Dix MR, Hallpike CS. The pathology, symptomatology and diagnosis of certain common disorders of the vestibular system. Proc Soc Med 1952;45:341-354.
  19. Dix MR, Hallpike CS. The pathology, symptomatology and diagnosis of certain common disorders of the vestibular system. Ann Otol Rhinol Laryngol 1952;61:987-1016.
  20. Canavan M. Schilder’s encephalitis perioxalis diffusa. 1931.
  21. Hurler, G. Über einen Typ multipler Abartungen, vorwiegend am Skelettsystem. Zeitschrift für Kinderheilkunde. Berlin. 1919;24: 220–234.
  22. Pfaundler M. Demonstrationen über einen Typus kindlicher Dysostose. Jahrbuch für
    Kinderheilkunde und physische Erziehung, Berlin, 1920;92: 420.
  23. Hunter CA. A rare disease in two brothers. Proceedings of the Royal Society of Medicine, London, 1917, volume 10, Section Dis. Children, 104-116.
  24. Frey L. Le syndrome du nerf auriculo-temporal Rev Neurol (Paris) 1923;2:92-104.
  25. Walker MB. Myasthenia gravis: a case in which fatigue of the forearm muscles could induce paralysis of extra-ocular muscles. Proc R Soc Med 1938;31:722.
  26. Walker MB. Treatment of myasthenia gravis with physostigmine. Lancet 1934;1:
    1200–1201.

A Report from the International Congress on Parkinson’s Disease and Movement Disorders

WFN Junior Traveling Fellowship Award Recipient

By Wael Ibrahim

Wael Ibrahim presented his poster, “ Epilepsy and Cranial Nerve Affection in a Patient With Wilson’s Disease and Intracranial Developmental Venous Anomaly,” at the 21st International Congress of Parkinson’s Disease and Movement Disorders meeting.

The 21st International Congress of Parkinson’s Disease and Movement Disorders was held June 4-8 in Vancouver, BC, Canada. The congress was organized by the International Parkinson and Movement Disorder Society. The purpose of the International Parkinson and Movement Disorder Society is promotion of research and education on Parkinson’s Disease and Movement Disorders, to improve the care for patients who have Parkinson’s Disease and other Movement Disorders, and to facilitate the dissemination of information regarding movement disorders.

Skills and teaching courses held during the congress were an excellent opportunity to share and exchange scientific ideas and improve our education and experience. It is always great to attend the lectures and discussions on ongoing research projects, hear lectures on the most interesting topics, and provide an opportunity for networking.

It was an honor to present the results of my case report as a poster presentation, “Epilepsy and Cranial Nerve Affection in a Patient With Wilson’s Disease and Intracranial Developmental Venous Anomaly: A Case Report.” To our pleasure, we received several interesting questions and remarks from colleagues and field experts about the study design and data interpretation.

Overall, attendance at the congress was successful and helpful for my future development as a clinician and researcher. Attendance at the Congress was kindly supported by the WFN. I want to express my gratitude and happiness for this great opportunity. Great thanks and best wishes to all members of WFN.

Wael Ibrahim is from the Kasralainy Faculty of Medicine at Cairo University in Egypt. www.kasralainy.edu.eg

A Report on a Visit to Sleep 2017 in Boston

WFN Junior Traveling Fellowship Award Recipient

By Oluwatosin Olorunmoteni

I am delighted to present my report on Sleep 2017. I had the privilege of attending this meeting through the sponsorship provided by the WFN as a recipient of a Junior Traveling Fellowship Award.

Oluwatosin Olorunmoteni at Sleep 2017 in Boston, Massachusetts.

Sleep 2017 was the 31st annual meeting of the Associated Professional Sleep Societies, LLC (APSS) comprising the Sleep Research Society (SRS) and the American Academy of Sleep Medicine. Although I developed interest in pediatric sleep medicine during the course of my training in pediatric neurology, I have not been able to take formal training in sleep medicine or attend a conference on sleep. I am exceedingly grateful to the WFN for making this dream come true.

Sleep 2017 was held June 3-7 at the Hynes Convention Center in Boston, Massachusetts. It was an educational and impactful experience for me.

On Saturday, June 3, I attended a half-day postgraduate course on EEG Essentials for the Sleep Practitioner. Following that, I had the privilege of participating in the SRS Leadership Workshop. The educational programs organized by SRS continued on Sunday, June 4, with the Trainee Symposia Series. These two trainee development programs by the SRS were my best sessions at the meeting as I had the privilege of meeting and learning from leaders in the field of sleep medicine. I also had opportunities of networking with colleagues.

Oluwatosin Olorunmoteni presented her abstract.

I presented my abstract on Monday, June 5. More than 1,200 abstracts were presented at Sleep 2017.

The abstract presentation afforded me the opportunity to meet specialists and colleagues in sleep medicine working on similar research areas. I also met a number of Nigerians in the diaspora. They suggested many ideas that can improve my future research. I also discussed the need for a sleep lab in my institution with many of them, and they offered useful suggestions on the way forward.

Sleep 2017 had many educational opportunities, which were highly beneficial especially for young professionals like me. There was never a dull moment as I attended sessions that included Invited Lectures, Conversation with Experts, Symposia, and Oral and Poster Presentations. I learned a lot from the pediatric sleep sessions, where discussions on actigraphy, pediatric narcolepsy, school start times, and parasomnias were discussed.

A major benefit of attending Sleep 2017 for me was the opportunity to visit the Boston Children’s Hospital where I saw the sleep lab. It further increased my quest to intensify efforts to get a functional sleep lab in my institution.

Despite the rainfalls, I was able to visit downtown Boston during the week. I also joined SRS trainees for a time out at the kickball game on Saturday.

I left Boston on Wednesday, June 7. I felt excited and fulfilled because Sleep 2017 was my best conference ever! I am grateful to the WFN for giving me this opportunity. 

Oluwatosin Olorunmoteni is from Obafemi Awolowo University in ILE-IFE, Nigeria.

Peripheral Nerve Society Meeting in Sitges, Spain

Mitochondrial transport down dorsal root ganglion axons is impaired by saturated fatty acids, a likely mechanism leading to energy loss and axonal neuropathy in Type 2 diabetes. The slide is from a lecture from Prof. Eva Feldman’s lab.

The 13th Congress of the Peripheral Nerve Society (PNS) took place July 8-13, in Sitges, Spain. The PNS hosts annual congresses, and the next congress will be in July 2018 in Baltimore, Maryland. In 2019, it will take place in Genoa, Italy.

For the International Congress on Neuromuscular Diseases (ICMND) 2018 in Vienna, the Neuromuscular Congress of the Research Group on Neuromuscular Disease of WFN, it is planned that a joint session of the PNS and ICNMD will take place.

The Congress of the PNS is devoted to the peripheral nerves, not only on clinical entities, but building the gap between basic research and toward the clinical implications.

This year, there were 500 participants from more than 50 nations. The PNS has a strong emphasis on education, and about 100 young participants were sponsored to attend the meeting in order to present posters and platform presentations.

The scientific content contained many basic and translational aspects, such as the molecular aspects of node of Ranvier, the metabolic support of axons by Schwann cells, and the new models of auto-immunity to nodal components. Also, pain and ion channels were discussed in plenary lectures.

Sitges, Spain, proved to be an attractive site for the Peripheral Nerve Society Meeting with excellent meeting facilities and attractive beaches.

One of the concerns of the PNS is the research and treatment of inflammatory neuropathies. Treatment studies and open questions were discussed. Another important aspect is diabetic neuropathy, where worldwide an increase of diabetes as a noncommunicable disease is being observed. Mechanisms and possible treatments were discussed. The role of changing food habits, lack of exercise, and lifestyle seem to contribute to this development. A future strategy in a worldwide campaign against diabetic neuropathy was initiated.

Several papers and posters addressed issues of genetic neuropathies. Increasingly, chemotherapy-induced neuropathies are attracting attention, not only in regard to prevention, but also pain treatment and management.

Neuropathic pain was a topic, and ion channels, particularly the PIEZO2, STOML3 channel, were explained and discussed. They will have an impact on our understanding of neuropathic pain. Also, the poster sessions contained several reports on treatment of neuropathic pain.

Daily poster sessions were filled with attendees. Many discussions and interactions took place. Many interesting and often rare observations were displayed and discussed. For scientific papers and merits, traditional prizes (as, for example, the PK Thomas prize) were awarded by the PNS.

In the final ceremony, Steven S. Scherer took over the presidency from Mary M. Reilly.

The congress was held in a nice venue–the Melia Hotel Sitges. Traditionally, as is familiar to all PNS meetings, the atmosphere was good and open, and interactions were encouraged. It was excellently organized, and provided a useful platform to exchange ideas and to engage in networking.

25 Years of Russian-German Neurological Cooperation

By Profs. Peter Wolf and Alla B. Guekht

Inauguration photo from the association’s founding in 1992. Front row from the left: Profs. Peter Wolf, F. Manz, K. Schimrigk, Levon Badalyan, E. Gusev, and B. Guekht.

A meeting on Diseases of the Nervous System — Mechanisms and Treatment was held April 6-7 in Moscow to celebrate the 25th anniversary of the Association for Promotion of German-Russian Cooperation in Neurology.

This association, whose name was later changed to the Russian-German Neurological Society, is perhaps not well known in global neurology, but played an important role in the first period after the European system shifts of 1989-1990. Until then, for about half a century, there had been extremely few possibilities for neuroscientists of West Germany and the Soviet Union to meet and exchange their views or to publish in each other’s journals.

The scientific developments on both sides of the Iron Curtain often  went different ways, and the post-World War II generations in East and West took little notice of each other. This was quite a change from earlier traditions, and symptomatic of the general disruption within Europe.

The new possibilities were first explored by Prof. Jefim Salganik of Gütersloh, a German neurologist who was born in the Soviet Union and had studied medicine in Moscow. He contacted and then visited Prof. Levon Badalyan of Moscow, who had been an opponent for his doctoral thesis.

In consequence, a visit of a group of neurologists from northern Germany was organized in February 1991. They met with a group of leading Russian neurologists and their disciples for a seminar, which was held in Moscow and Yaroslavl, Russia. It became an unforgettable experience for all participants. Transportation, lodgings, translations, and meeting facilities, including something as unusual at the time as video demonstrations, needed a lot of improvisation.

All difficulties were overcome by the local organizers, and the hospitality was overwhelming. There was great mutual curiosity about the methods and traditions that had developed, and time set aside for discussion was never sufficient. Thus, the last papers were delivered and discussed on the bus, as all drove back together to Moscow through the white winter landscape. It was one of the occasions where enduring friendships arise among people who until then had been foreigners to each other.

Both sides expressed a strong interest in establishing a platform for future exchange and meetings. Also, in the German group, many were strongly aware of Nazi Germany’s barbarous actions, especially in Eastern Europe. The German group found it their duty to be the first to reach out to Russian colleagues and integrate them into the common European agenda.

When in 1992 the Russian group was received in Germany for a second scientific encounter, the association was founded and registered in Germany, where it also came to function as a commission of the German Neurological Society. Leading neurologists from both countries (Profs. Badalyan, Gusev, Guekht, Schimrigk, Wolf, Haass, Salganik, Manz, and many others) contributed to the establishment and further development of the society.

In the following years, annual meetings alternating between the two countries took place, and informal fellowships for the training of young neurologists were privately organized. More colleagues became interested and joined the society. Over the years, as international contacts and exchange possibilities multiplied, the general meetings lost their uniqueness
and became rarer. However, in some subspecialties, bilateral cooperation intensified and deepened, especially in stroke, epilepsy, and neuromuscular diseases, where several early association members became national and international key players.

The 25th anniversary meeting was a welcome occasion to update newer research and to remember an initiative reflecting very well the spirit and optimism of the early 1990s, which definitely made a change for European neurology. 

Prof. Peter Wolf is from Dianalund and Florianópolis, and Prof. Alla B. Guekht is from Moscow.

Report of the Department Visit Program to Turkey

By Dr. Leonard Ngarka

From right to left: Prof. Recep Aygul, Prof. Serefnur Öztürk, Dr. Hakan Ekmekci, Dr. Leonard Ngarka, medical students, and Resident Dr. Azer Mammadli, during ward rounds.

I was delighted when I received the news of my selection for the WFN-Turkish department visit program in October 2016. It didn’t actually take place until Feb. 18, 2017, due to visa procedures. I am grateful to Prof. Alfred Njamnshi and Prof. Serefnur Öztürk, as well as Burak Tokdemir, who facilitated my visa acquisition.

I arrived at the University of Selcuk, University Faculty of Medicine in Konya, Turkey, on Feb. 17, and immediately settled into my accommodations. The next day, I was warmly received by the staff of the Neurology Department under the leadership of Prof. Öztürk, who presented the service. I was handed a detailed program for my stay there. Each working day ran from 9 a.m. to 5 p.m., with a break between noon and 1:30 p.m.

During the four weeks, I spent each day from 9 a.m. to noon seeing patients hospitalized in the department, including those in Neurointensive Care. For the first week, the period from 1:30 p.m. to 5 p.m. was spent in outpatient consultation with the different consultant neurologists, and we received 18-25 follow-up cases and six to eight new cases per day. This exposed me to the manipulation of recent drugs and protocols in the management of patients with neurological disorders.

Selcuk University Faculty of Medicine, Neurology Department team, including all staff in front of the Neurology Department (in-patient service).

The remainder of my afternoons were spent in clinical neurophysiology labs: EMG, EEG, and polysomnography labs for the second, third, and fourth weeks,  respectively. I carried out nerve conduction studies on patients who came during this period and did a good number of needle EMGs. All of these were conducted under the supervision of Prof. Recep Aygul and Dr. Hakan Ekmekci. My participation in the EEG sessions has improved my reading and interpretation of EEGs, especially video and sleep EEGs. During the last week of my stay, I had introductory lessons on evoked potentials and polysomnography, of which I did a few and assisted in their interpretation.

I participated in several staff meetings with other departments, including with neuroradiology and interventional radiology specialists to discuss cases of carotid artery stenosis; with endocrinologists, and ear, nose, and throat specialists to discuss the management of patients with sleep disorders; and with the department of psychiatry. There were other presentations in the department among residents and students, and I made a presentation on peripheral nerve disease and entrapment neuropathies.

My experience in Turkey was exceptional, and the memories will last long. It was an exposure to up-to-date science, to culture, and a challenge to pursue excellence. This visit has significantly impacted my clinical practice. I have adapted some of the protocols from Konya (Parkinson’s disease and other movement disorders) in patient care back here in Cameroon. I am presently assisting in doing EMGs in a hospital close to ours in order to continue the training and keep the skills I acquired.

Even though insufficient infrastructure, equipment, and drug availability remain a major setback in Africa, one thing stands: quality training is the bedrock for research and quality patient care and development on this continent. This visit has contributed to improving the quality of my training. 

I wish to express my heartfelt gratitude to the World Federation of Neurology, the Turkish Neurological Society, and the Neurology Department of Selcuk Medical Faculty for giving me this opportunity. I wish to thank Profs. Öztürk and Aygul, Dr. Ekmekci, and the neurology residents and staff of this department for making my stay memorable.

In Memoriam: Prof. Franz Gerstenbrand (1924-2017)

We have the sad duty of sharing the news of the passing of Prof. Franz Gerstenbrand.

Prof. Franz Gerstenbrand

Franz Gerstenbrand was born in 1924 in Hof (Moravia, Czech Republic). He completed his medical training in only four years under difficult post-war circumstances in Vienna. His specialty training was at the Psychiatric-Neurological University Department of Vienna University Hospital (Psychiatrisch-Neurologische Universitäts-Klinik Wien), chaired by Prof. Hans Hoff. As a pupil of Prof. Hoff, Prof. Gerstenbrand had great interest in traumatic brain injury and was the first to initiate a unit for traumatic brain injury treatment in Vienna. He also had a keen interest in child neurology.

In 1967, Prof. Gerstenbrand published his habilitation treatise on traumatic apallic syndrome, Das Traumatische Apallische Syndrom. This book for many years was regarded as standard literature on traumatic vegetative state in German-speaking countries, and it made him well known in Central Europe.

Franz Gerstenbrand months before becoming a medical student in Vienna.

Prof. Gerstenbrand was appointed in 1976 as first chair to the University Clinic for Neurology in Innsbruck. He quickly recognized the upcoming needs and advantages of subspecialities within neurology. In the following 18 years, he helped initiate numerous subspecialities, including neurointensive care, neuroimaging, and caring and advocating for stroke patients. All of those initiatives were innovative in the second half of the 1970s. His decisions laid the foundation for the outstanding reputation of the University Clinic for Neurology in Innsbruck.

He was an active clinical researcher, publishing more than 780 papers. He also co-edited 12 textbooks and monographs.

Prof. Gerstenbrand was involved in many international collaborations, including one with the Institute for Biomedical Problems, Moscow, which led to the first Austrian-Russian space neurology collaboration. His team developed a series of experiments that were performed by a number of cosmonauts, including the first and only Austrian cosmonaut, Franz Viehböck.

In 1962, he initiated the Danube Symposium — a clear-sighted decision to bring together East and West European neurology. His strong belief was that Central and Eastern European neurology needed to be represented with a single voice. The Danube Symposia are still held each year.

Networking

Dr. Gerstenbrand (second row on the far left) at the Psychiatric-Neurologic University Clinic.

Throughout his life, Prof. Gerstenbrand advocated networking and collaboration within neurology. In 1991, immediately after the fall of the Iron Curtain, his strong advocacy and initiatives resulted in the foundation of the European Federation of Neurological Societies (EFNS), and he served as its first president. Those efforts were supported by Lord Walton, who at that time served as WFN president. EFNS was exceptionally successful, bringing together neurologists from all European countries. Part of the success was his strong belief that all European countries should have access and equal status in the organization. The EFNS was followed by the European Academy of Neurology.

As specialist with his teacher, Prof. Hans Hoff.

Until recently, his thoughts and efforts were directed in supporting areas of the world that lacked neurologists, and where training was needed. His last efforts were directed in supporting areas in Asia and Africa. For many decades, he had strong cooperation with Myanmar. Only days after his funeral, colleagues from Austria traveled to Myanmar to teach an initiative he was arranging in his last weeks. As he had foreseen many neurology developments, Prof. Gerstenbrand had foreseen his own death. In his last weeks, he made arrangements for his funeral and bought a grave at the same cemetery near the grave of Hans Hoff, his admired teacher.

Prof. Gerstenbrand has received numerous awards, including honorary doctorates from Charles University in Prague and Aristotle University of Thessaloniki, the Valeriy Gagarin Medal of the Russian space organization, and several of the most prestigious medals in Austria.

His life was dedicated to advocating neurology, and many of his pupils have been successful clinicians, leaders, and advocates. Prof. Gerstenbrand was a model for generations of neurologists in Central Europe.

We express our condolences to his wife Gudrun, his children, and his grandchildren.

Update on the Kasralainy Stroke Unit at Cairo University

By Prof. Ahmed Abdelalim

A stroke physician and assistants performed a transcranial duplex.

Egypt has the 15th largest population in the world, with approximately one-quarter of its citizens clustered in its capital, Cairo. Stroke medicine in Egypt has been facing many difficulties with implementation due to the economic problems and an inadequate number of stroke neurologists.

Kasralainy Medical School is the largest medical center in the Middle East, with a capacity of over 5,000 beds providing medical services to more than
2 million people per year, half of which are served in the emergency department. The first stroke unit was established over 20 years ago, but could not satisfy the need due to the rapidly growing population and difficulties with the insurance system.

The plan for a new stroke center was then created with great ambitions of going beyond offering medical services to providing stroke training and research opportunities to Egyptian, African, and Middle Eastern neurologists and to help raise community awareness. Over the years, the neurology department has sent many of its young members to European stroke centers, through grants, to be trained on modern stroke medicine together with in-house training on advanced life support and neurocritical care skills. Today, these neurologists have become the core of the new stroke unit and trainers to their younger colleagues.

The stroke team, including stroke nurses and administrative personnel.

In 2010, the hospital administration granted the place and funds to establish the new stroke unit. Due to the political circumstances in 2011, the project was halted until 2015, when the Kasralainy administration, led by Prof. Fathy Khodair, dean of the medical school, showed a great interest and determination to fulfill the project. In August 2016, the stroke unit was ready for a new start.

The new stroke unit has a capacity of 36 beds, which includes 14 intensive care (with ventilation capability), 14 intermediate care, four isolation, two thrombolytic therapy, and two resuscitation beds, with the capacity of providing thrombolytic stroke therapy concurrently for four or more patients. This makes the unit the largest high-dependency stroke unit in the Middle East fully run by neurologists, offering thrombolytic therapy and thrombectomy to all Egyptians free of charges. The unit provides advanced acute stroke treatment services, including neurosurgery, neurointervention, advanced neuroimaging, and neuro-rehabilitation for 1,500-2,000 patients per year.

The Kasralainy Medical School stroke unit.

The opening of the new stroke unit received another boost thanks to the new policy on supporting and promoting stroke medicine, together with the efforts of the Stroke Chapter of the Egyptian Society of Neurology, Psychiatry, and Neurosurgery to coordinate between stroke units on a national level and promote the use of guidelines and hospital-based registries. The training and research opportunities are further supported and extended by the WFN accreditation of the neurology department at Cairo University as a training center for English-speaking African neurologists.

The ongoing “revolution” of stroke medicine in Egypt has made the floor ready for great success for the new stroke treatment policy, with a better acute stroke treatment service and reduction of the national and regional burden of stroke. The new Kasralainy stroke unit is ready to play its leading role. 

Prof. Ahmed Abdelalim is the director of the Stroke Unit, Faculty of Medicine at Cairo University.

The Need for World Congresses

By Raad Shakir

Raad Shakir, MD

Reasons for attending and participating in congresses vary. There are those who like to travel and meet neurologists from other parts of the world, which they will never do even if they visited their countries. There are others who are attracted by the lure of the big names of speakers, the organizing associations, and the attractiveness of the cities. For world congresses, the attendees come in the thousands because the meetings transcend national, regional, or specialty categories. This means that there is something for everyone. 

If you look at national neurological society meetings, they tend to have few outside speakers, but the attendees are colleagues, perhaps in the same institution or the one next door. You tend to know most attendees, and it serves not only to listen to what others are doing in their research or how they practice, but to hear about gossip and job opportunities and to obtain postgraduate certification.

Perhaps another advantage/disadvantage is that of language. Many national meetings are in the local language, which is well and good. The advantage is that neurologists will have a better understanding of what is being said and will be clearly advised on practice parameters and guidelines. On the other hand, the language of medicine and science is English and many national associations’ congresses will either have sessions in English or have completely changed their language to English. 

The reasoning is clear. If a neurologist or a neuroscientist would like to publish internationally, then the only way to get a recognized indexed paper is to use the English language. 

In essence national congresses are all well and good, but they lack an international outlook and global interaction.

The second level is that of major regional international associations’ congresses, which are geographically distributed. There are six such congresses; two are annual and four are biennial. Some of these are well attended and professionally organized. However, in some regions with nascent associations, the concepts are still developing. The big regional organizations’ congresses are attended from outside their regions, and this is important for interaction. Such organizations certainly encourage work to be presented as well as out-of-region attendance to boost their figures and standing.

Looking at the plethora of specialty meetings and congresses, they obviously concentrate on specific topics. The degree of interest varies enormously. The speakers are obviously well known in their fields, but perhaps at times tend to concentrate on fine detail, which may not be of major interest to the audience. The attendance by and large relies on support from various sources to register and travel. The major advances in the specific field tend to be presented. Even if the neurologist is interested in the field in question, after a day or so the topics become a bit repetitious and some, if not the majority, will lose interest.

Specialty congresses, however, have a pivotal role to play in educating not only neurologists, but to propagate neuroscience in specific fields. Scientists may not have the funds to attend big international jamborees as their travel funds come from grants that rightly limit their ability to travel. Over the last decade or two, there has been an explosion in attendance of other health care professionals who find attending specialty meetings vital. Nurses, therapists, pharmacists, and psychologists, to name a few, all need to listen to advances in their chosen field of specialty. These fields tend to be by and large covered in specialist congresses. The majority of such practitioners will shy away from large general international congresses.

Drug industry-sponsored congresses and meetings tend either to be directed at a local group of medical practitioners or a targeted audience chosen by the sponsors. Governmental rules are rightly restricting sponsorship because public opinion is clearly against such practices. There is certainly a place for informing neurologists on the availability of certain drugs in their locality, and there is definitely a role to be played by the pharmaceutical industry. However, this has to be limited and controlled, rather than left to a self-governing code of practice.

In many parts of the world, governments will forbid pharmaceutical company sponsorships within the same country. As an example, if a meeting on a specific topic is being organized in a certain city, only neurologists from that city and not from other parts of the country, let alone internationally, can be sponsored to attend.

Presentations in pharmaceutical industry-sponsored meetings and symposia are primarily viewed as being at least partially one-sided. The majority of speakers declare their financial interests and do their best to provide non-biased views in their presentations. However, we cannot escape the fact that neurological public opinion tends to take the presentations with a pinch of salt. Even at major international congresses, sponsored symposia are separated from the main themes of the congress and portray a different point of view.

We have to remember another issue of funding congress attendance. In many parts of the world, the neurologist, as well as any other medical practitioner, can claim tax relief on congress attendance as part of the annual continuing medical education (CME) requirement. This practice in some localities is limited by governments to national meetings, and in some instances to international congresses, which carry certificates of approval from major international medical institutions. This practice has to be strict, as it deprives governments from taxation.

As you are all probably aware, the upcoming 23rd World Congress of Neurology (WCN) is being held Sept. 16-21, 2017, in Kyoto, Japan. We are all grateful for the Japanese Society of Neurology for hosting us. This is the showcase of global neurology. The biennial nature of the congresses makes them that bit different, and the general nature of the program is an attraction to many. The basic principle is to involve all six regional organizations and all of the specialties in neurology. Each one is asked to provide a program with conveners and speakers so that the essence of the specific field is distilled into one congress. Moreover, each congress is hosted by a national neurological society, and the competition is quite fierce. Holding the WCN is a privilege to the national society and its region. Congresses bring benefit to the society and the region. This has been seen time and again.

The WFN makes sure that our congresses are not, in the old sense, carbon copies, but have a basic structure and a distinct local flavor. Kyoto is no different. The Asian region’s competition was fierce, but the WFN council of delegates voted to award the congress to Kyoto. The WFN system of egalitarian democracy is unique in that the WFN leadership can only watch the delegates vote and decide. The choice and the decision is theirs.

Once the decision is made, the WFN works closely with the host society to produce the scientific program, teaching courses, and social programs. The role of the WFN and its congress organizer is to closely advise the host society on how the whole congress is constructed using previous experience, but adding a local touch.

The WCN is therefore a balanced and an appetizing mixture of all types of congresses — national, regional, specialty, and industry-sponsored meetings. The attendee is presented with the best of several worlds in a concise and a most perfectly packaged setting.

There is no doubt that it is a unique opportunity. I urge all of you to attend.