Letter from the Editors

Steven L. Lewis, MD, Walter Struhal, MD

We would like to welcome all neurologists worldwide to the September/October 2021 issue of World Neurology. The issue begins with the President’s column, where WFN President Prof. Bill Carroll discusses the upcoming WCN, opening within days of the publication, and the important role of the WCN in the WFN.

Next, Kimberly Karlshoej, WFN strategy and program director, and on behalf of multiple contributors, updates us on the Intersectoral Global Action Plan (IGAP) on Epilepsy and Other Neurological Disorders of the WHO.

Prof. Wolfgang Grisold provides another informative report on the WFN Committees and Specialty Groups, with this issue’s report providing us with an update on the Constitution & Bylaws Committee and the Neurosonology Specialty Group. Prof. Gagandeep Singh and colleagues then discuss their recent publication of the India State-Level Disease Burden Initiative, reporting on the trends of the burden of neurological diseases across the states of India from 1990 to 2019.

Dr. Imane Hajjaj, from Morocco, provides us with a report of her successful and informative (pre-COVID-19) visit to Istanbul, Turkey, as part of the WFN Department Visit program. In this issue’s History column, Prof. JMS Pearce discusses the development of the concept of the extrapyramidal system. Next, María Jimena Alemán, a medical student from Guatemala, reviews the book One by One by One, by Dr. Aaron Berkowitz, about the author’s experience providing much-needed neurologic care in Haiti.

Finally, Dr. David Steinberg provides a heartfelt obituary, reprinted with permission from the Journal of the Neurological Sciences, on the life of Dr. George K. York III, neurologist and historian of neurology.

Thank you for your interest in World Neurology, and we look forward to “seeing” so many of you at the WCN2021, starting Oct. 3! •

George Kenneth York III

David A. Steinberg

George Kenneth York III]

George Kenneth York III]

George K. York III, neurologist, historian of neurology, and health care executive, died in Fiddletown, California, June 14, 2021, at the age of 70 after a protracted series of medical adversities.

York was a skilled clinician, world-renowned historian, creative writer, and expert in finance and audit. He was a concerned and empathetic physician who saw his clinical role primarily as a patient advocate.

His accomplishments in his parallel life as an academic historian of neurology included chairmanships of the history sections of the American Academy of Neurology and World Federation of Neurology, twice winner of the AAN’s Lawrence McHenry Award, many invited international lectures, dozens of peer-reviewed publications, and memberships in the Royal Society of Medicine and Savile Club.

York’s area of academic focus was the life and work of the founder of scientific neurology, John Hughlings Jackson, for which he was the acknowledged world’s expert. His myriad academic accomplishments aside, York may have been most proud of his creative writing. His humorous commentary on health care issues and policies, called The Termite, was distributed every week for nearly 15 years to the Kaiser Medical Group.

He also was awarded the AAN’s creative writing prize. Additionally, York was blessed with a keen business acumen being a member of the AAN finance committee and chair of Kaiser’s finance and audit committee for many years.

York was born in Palo Alto on Sept. 7, 1950, while his father was a graduate student at Stanford University and grew up in Davis, California. He attended college for a year at the University of San Francisco and graduated from University of California, Riverside with a BS in chemistry.

While applying to medical schools, York did research in pulmonary physiology at the UC Davis Medical School and matriculated with the UC Davis Class of 1978. He did his internship in internal medicine at UCLA and completed his neurology residency at UC Davis.

After a research fellowship at UCSF, York opened a private practice in Placerville and Jackson in California’s Gold Country. After two years, he was recruited to head the neurology department at Kaiser Stockton, and for nearly the rest of his clinical career, he was chair of the department and elected representative for Stockton on the Kaiser Board of Directors.

His intelligence, knowledge, incisive humor, and devotion to his friends and family will be sorely missed by all who knew him.

York is survived by his wife Pamela and his siblings, Judi Williams, Peter York, Jennifer Linzey, and Melissa Chase. •


This In Memoriam is reprinted with permission from the Journal of Neurological Sciences, June 2021. David A. Steinberg, Fiddletown Institute.

Estimating Subnational Neurological Disease Burden: A Worthwhile Mission

By Gagandeep Singh, MV Padma, Pramod Pal, Jeyaraj Pandian, PN Sylaja, Suvarna Alladi, and Lalit Dandona

Gagandeep Singh

Gagandeep Singh

The burden of neurological diseases as measured by disability adjusted life years (DALYs) and years of life lost is an invaluable piece of information for many. Among the many are health care policy makers, academic institutions, and neurological health care providers. The India State-Level Disease Burden Initiative recently published trends of the burden of neurological diseases across the states of India from 1990 to 20191.

India is seventh largest in terms of area among all countries in the world. It has a population of nearly 1.4 billion, second highest after China, and is slated to be the most populous nation in the world by 2025. The country is geographically divided into 28 states and eight union territories. The per capita gross domestic product of India is US$ 2,100, with a ten-fold variation between the states and union territories. Arguably, therefore, considerable variation is expected in terms of socio-demographic standings, income, and cultural and ecological characteristics between the states of India. Inherent, e.g., genetic, differences are also likely to exist between different subpopulations within the country. Predictably, therefore, disease burdens including those of neurological disorders are likely to vary across the states.

The neurological diseases burden across the states of India, 1990-2019, not only underscores the geographical disparities across India but also the temporal trends in the burden of all neurological diseases combined and a range of neurological disorders1. Overall, neurological disorders accounted for nearly a tenth of DALYs for all diseases combined in India. This proportion increased somewhat between 1990 and 2019; from 8.3% to 9.9%. Remarkably, however, over the same time period, the point estimate of the contribution of non-communicable neurological disorders to DALYs from all causes increased from 4.0% to 8.2%, i.e., doubled.

As distinct from this trend, the proportion of communicable neurological disorders including meningitis, encephalitis and tetanus decreased from 4.1% to 1.1%, i.e., nearly four times. Aside from these two major subgroups of neurological disorders, the contribution of injury-related neurological disorders increased from 0.2% to 0.6%, representing a three-fold increase.

These data are testimony to the epidemiological transition taking place in the country. Over the decades since the Indian independence in 1947, it was assumed that communicable disorders, meaning thereby neurological infections, were the major predicament for Indian health care policy makers and care providers. This is changing and we need to be mindful of this evolution. The increase in injury related DALYs, likely a reflection of increasing use of vehicular transport, is also concerning as it is a largely preventable cause of enormous neurological morbidity and mortality.

The considerable variation in the neurological burden and of the incidence or prevalence and DALYs attributed thereof between the states of India is relevant as health is a state subject in India. Individual states, henceforth, need to prioritize their health care budgets, programmatic undertakings, and health care personnel training slots according to these data. The DALYs of communicable neurological disorders correlate inversely and those of injury-related neurological disorders varied directly with socio-demographic development indices of various states, while there is no such correlation in the case of non-communicable disorders. Subnational or within-country variations in the neurological burden are perhaps relevant to low- and middle-income countries and among them, for the most part to countries with large land areas with multi-ethnic populations, for instance, India and China. In China, likewise, there are remarkable socio-demographic variations between the industrialized east and the agrarian west and these may plausibly impact disease burdens and health care.

How does the neurological disease burden data from India compare with global numbers and proportions? Globally, the top five neurological disorders in terms of proportional contribution are stroke, migraine, Alzheimer’s and other dementias, meningitis, and epilepsy in that order2. Distinct from this, the order in India is as follows: stroke, migraine, epilepsy, cerebral palsy, and encephalitis (Alzheimer’s and other dementias and traumatic brain injuries closely follow encephalitis).

Encouraging to note, the incidence of, and age-standardized DALYs due to, stroke have somewhat declined between 1990 and 2019. This may reflect better preventative care implementation, leading to a reduced incidence and improved treatments in the form of specialist stroke units across the country. The age-standardized point estimates for the prevalence of epilepsies, cerebral palsy, Parkinson’s disease, multiple sclerosis and motor neuron disease have increased markedly. This probably could be attributed to a closing diagnostic gap but also, in case of epilepsies and Parkinson’s disease, increased longevity of the Indian population with time.

In comparison, the increase in prevalence for Alzheimer’s and other dementias is relatively modest, indicating perhaps that a considerable diagnostic gap still exists for this disorder. Inconsistent with the increase in prevalence of epilepsies and Parkinson’s disease, the age-standardized DALY rates attributed to these two neurological disorders have decreased over the past three decades. These surely signal progress in terms of closing the huge treatment gap and improved awareness for the two disorders.

Taken as a whole, the burden of neurological diseases across the states of India provides new information, which is both concerning and reassuring. These data call for a different level of preparedness to respond to the neurological disease burden in India. Moreover, the data call to attention subnational variations, and hence, should be a worthwhile exercise for neurological and epidemiological experts collectively in different nations constituting the membership of the World Federation of Neurology. •

References

  1. India State-Level Disease Burden Initiative Neurological Disorders Collaborators. The burden of neurological disorders across the states of India: the Global Burden of Disease Study 1990-2019. Lancet Glob Health. 2021 Aug;9(8):e1129-e1144. doi: 10.1016/S2214-109X(21)00164-9.
  2. GBD 2016 Neurology Collaborators. Global, regional, and national burden of neurological disorders, 1990-2016: a systematic analysis for the Global Burden of Disease Study 2016. Lancet Neurol. 2019 May;18(5):459-480. doi: 10.1016/S1474-4422(18)30499-X.

Gagandeep Singh, MD, DM, FAMS, FRCP is Professor & Head, Department of Neurology Dayanand Medical College Ludhiana, India &  Hon. Assoc. Professor Department of Clinical & Experimental Epilepsy Institute of Neurology Queen Square, London.

Kinnier Wilson and the Extrapyramidal System: An ‘Unknown Centrifugal Pathway’

By JMS Pearce MD, FRCP

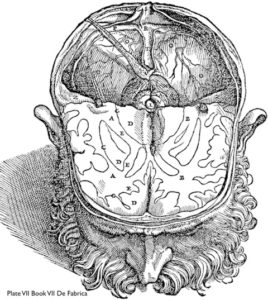
Plate VII, Book VII, Vesalius’s ‘De Fabrica’

Plate VII, Book VII, Vesalius’s ‘De Fabrica’ from https://www.researchgate.net/figure/Andreas-Vesaliuss-depiction-of-the-basal-ganglia-This-reproduction-of-plate-VII-of-book_fig1_276048418

In his De Humani Corporis Fabrica (1543), anatomically Andreas Vesalius distinguished the subcortical nuclei of the corpus striatum from the cortex and white matter, but he neither named them nor suggested their possible functions.

The corpus striatum was named by Thomas Willis (1621–1675), (whose birth quatercentenary we celebrate this year) in Cerebri Anatome (1664). He believed it was the source of motor functions, a view that persisted for almost 200 years.

The German anatomist and physiologist Karl Friedrich Burdach (1776-1847) provided more anatomical detail, but he had little idea about function, believing that the basal nuclei were responsible for sensory perception and consciousness. However, he differentiated the caudate nucleus (Streifenhügel) from the putamen (Schale). He also identified the substantia nigra (schwarzgraue), and the pale inner part of the lentiform nucleus that he called globus pallidus.

Before 1870, the motor function of the corticospinal pyramidal tract and the existence of an extrapyramidal system were not understood. The brain was simply the organ of consciousness, memory, and intelligence. The cortex was not known either to control or initiate motor function, not least because anatomists had not clearly delineated the anatomy or the physiology of the several descending tracts.

Electrophysiologically, Gustav Fritsch(1838-1927) and Eduard Hitzig (1838-1907) first showed the role of the pyramidal system, i.e. the motor cortex and its efferent tracts, in 1870. David Ferrier’s (1843-1928) classical ablation/stimulation experiments extended the results of Fritsch and Hitzig. He showed that Faradic stimulation of the cerebral cortex could produce movements and fits, and that cerebral functions were localized in definable discrete areas, which he mapped as sensory and motor across several species, thus defining cerebral localization.  Carpenter in 1874 ranked Ferrier’s cerebral localization “among the greatest advances in the physiology of the nervous system made in the last 50 years.”

As a concept, the extrapyramidal system (EPS) was first conceived indirectly by Johann Prus (of Lemberg, Galicia, now Lviv, Ukraine) in 1898. He discovered that experimental lesions in the pyramidal tracts failed to control induced cortical epilepsy. He unilaterally transected the pyramidal tract in dogs at the levels of the internal capsule, midbrain, pons, and medulla, and noted:

“Bilateral epileptic seizures occurred on stimulation of the cerebral cortex, on the same as well as the side opposite the operation… To explain the results of my experiments I had to assume that there is in the dog either bilateral innervation in the cortex, and that excitation spreads to the other hemisphere by means of the commissure fibres when the pyramidal tract has been cut, or that in this case conduction of cortical epilepsy takes place by means of a so far unknown centrifugal, i.e., motor pathway (Italics by JMSP).”

He deduced the presence of an unknown centrifugal motor pathway. But it was Samuel Kinnier Alexander Wilson (1878-1937) who was first to use the term “extrapyramidal” in its modern sense. His term extrapyramidal was adopted to distinguish between the clinical effects produced by damage of the basal nuclear tracts and those caused by damage to the classic pyramidal pathway.

Prus‘s 1898 publication in the Wiener klinische Wochenschrift

Prus‘s 1898 publication in the Wiener klinische Wochenschrift

In his 1912 classic paper Progressive Lenticular Degeneration (Wilson’s disease), he described the autopsy of three patients with this disease where he observed pathology outside the pyramidal system and named them extrapyramidal tracts:

“In spite of the great degree of motor weakness and helplessness, in a pure case [of hepatolenticular degeneration] the abdominal reflexes are preserved and a double flexor response is obtained.  … the problem lay outside of the pyramidal system, “ in other words, this affection, where it occurs in an uncomplicated form, is an extrapyramidal motor disease. … To distinguish these apparently motor pathways from pyramidal and pontine tracts we shall call them extrapyramidal tracts.”

Although he failed to define specific tracts anatomically, this was the first use of the term “extrapyramidal” in neurology literature. In this era, several others inferred a motor role for areas outside the pyramidal tracts. (See Table 1.) The Swiss neurologist (of Russian descent) Constantin von Monakow (1853-1930) delineated a rubrospinal tract and the Austrian neuropsychiatrist Baron Constantin von Economo (1876-1931) proposed that the substantia nigra was involved with motor control of chewing and swallowing; lesions of the substantia nigra and red nucleus of cats and monkeys induced choreoathetosis. The Russian neurologist Vladimir Bechterew (1857-1927) stimulated the substantia nigra in dogs and noted swallowing, changes in respiration, ocular and pupillary changes, and contraction of neck muscles.9

Before Wilson’s paper, the confusion about sites of pathology in the several extrapyramidal disorders is evident in James Parkinson’s (1755-1824) account of the disease he discovered in 1817; he mistakenly guessed it originated in the “medulla spinalis.” The pathology was then unknown, but in 1894 while studying paralysis agitans, Hermann Oppenheim (1858-1919), the foremost Berlin clinical neurologist, provided sufficient clinical evidence to establish the duality of motor control, and to infer the existence of both pyramidal and extrapyramidal tracts in motor function. He wrote:

“Resistance to passive motion is always present in the later stages, and often before that time. It differs from spastic rigidity [of pyramidal tract disorders] in that it is not increased by passive motion, but is constant and regular . . .”

William Alexander Hammond (1828-1900), a founder of American Neurology in A treatise on diseases of the nervous system of 1871 recognized athetosis and suggested: “One probable seat of the morbid process is the corpus striatum.” The Austrian neuropsychiatrist Gabriel Anton (1858–1933) in 1896 indicated the basal nuclei could cause a motor disorder when in childhood double athetosis he reported hypermyelinated lesions in the putamen, later named état marbré,

Wilson’s long classic paper11 pointed out that the EPS (extrapyramidal system) had a “steadying” influence on the anterior horn cells:

“the relation of the corpus striatum (basal ganglia) to the rest of the motor system is one of tone control, and of steadiness of innervation. . . . Remove its influence by disease, [then] tonic postures become overemphasized.”

His view of dual motor function, pyramidal and extrapyramidal, was quickly and widely accepted.

Extrapyramidal Disease

The term extrapyramidal disease now refers to a group of motor disorders associated with pathological alterations in the basal grey matter whose function is predominantly motor. Clinically, extrapyramidal disorders consist of one or a combination of the following phenomena:

  1. abnormal involuntary movements
  2. changes in tone of skeletal muscles with an increase or decrease in resistance to passive motion
  3. poverty or excess of movement
  4. alteration of automatic movements.

The two motor systems are linked both anatomically and functionally, with extensive feedback loops.

Anatomically, the striatal EPS is polysynaptic and consists of nuclei and fibre tracts that receives projections from the cerebral cortex and sends efferent subcortical pathways to the brainstem and cord. Extrapyramidal structures comprise the cerebellum, basal nuclei including the neostriatum — subcortical caudate nucleus and the putamen nuclei — plus the substantia nigra, red nucleus, and the subthalamic nucleus of Luys. From them arise subcortical extrapyramidal tracts that terminate in the spinal cord. The Tectospinal, rubrospinsal, reticulospinal, and vestibulospinal tracts were described within the two decades 1890-1910.

Functionally, the EPS maintains posture and regulates involuntary postural tone and movement. It also has a role in behaviour, learning and cognition. Medium spiny neurons are the principal neurons of the striatum. They are the efferent cells, projecting to both segments of the globus pallidus, ventral pallidum, and substantia nigra. GABAergic in function, they are of several subtypes, and contain dopamine receptors and cholinergic and GABAergic interneurons. Both pyramidal and extrapyramidal systems project in the descending white matter tracts. (See Table 1.)

The extrapyramidal motor disorders are well recognized in basal nuclear diseases. They include Parkinson disease, Huntington chorea, Sydenham chorea, multiple system atrophy, torsion dystonias, and progressive supranuclear palsy. Altered posture and tone generally accompany involuntary movements, both bradykinetic and hyperkinetic — recognizable as tics, tremors, myoclonus, ballistic movements, chorea, and athetosis. They often show clinically characteristic individual patterns.

Exhaustive classifications (ICD-10 codes G20-G26 Chapter VI): contain 38 pages that include: acute dystonic reactions, blepharospasm, neuroleptic malignant syndrome, oculogyric crises, akathisia, drug-induced Parkinsonism, and various dyskinesias. •

JMS Pearce MD, FRCP, is Emeritus Consultant Neurologist at the Department of Neurology, Hull Royal Infirmary. E-mail: jms.pearce@me.com

References

  1. Parent A. The History of the Basal Ganglia: The Contribution of Karl Friedrich Burdach. Neuroscience & Medicine 2012;03: 374-379. 10.4236/nm.2012.34046.
  2. Quatercentenary of Thomas Willis’s birth — Department of Physiology, Anatomy and Genetics (DPAG) (ox.ac.uk)
  3. Burdach KF. Vom Baue und Leben des Gehirns (Of Structure and Life of the Brain);1819 -1826. cited by Parent1
  4. Lanska DJ. Early Controversies over Athetosis: I. Clinical Features, Differentiation from other Movement Disorders, Associated Conditions, and Pathology. Tremor Other Hyperkinet Mov (N Y). 2013;3:tre-03-132-2918-1.
  5. Pearce JMS. Sir David Ferrier MD, FRS. J Neurol Neurosurg Psychiatry. 2003 Jun;74(6):787.
  6. Ferrier D. The Functions of the Brain. London: Smith, Elder, 1876, pp. 163-196. [dedicated to Hughlings Jackson.]
  7. Carpenter W. On the Physiological Import of Dr. Ferrier’s Experimental Investigations into the Functions of the Brain, West Riding Lunatic Asylum Med Reports 1874; 4: 1-23.
  8. Prus J. Ueber die Leitungsbahnen und Pathogenese der Rindenepilepsie [Pathways and pathogenesis of cortical epilepsy] Wiener Klinische Wochenschrift, 11 (1898), pp. 857-863 (Annotated translation by Willner & Kennard, 1948
  9. Louis ED. The Origins of the Term “Extrapyramidal” within the Context of Late Nineteenth- and Early Twentieth-Century Neurology, Neurophysiology and Neuropathology. The Journal of the History of Medicine and Allied Sciences, 1993. pp. 68-79
  10. Lee J, Muzio MR. Neuroanatomy, Extrapyramidal System. In: StatPearls. StatPearls Publishing, Treasure Island (FL); 2020.
  11. Wilson S.A.K., Progressive lenticular degeneration: A familial nervous disease associated with cirrhosis of the liver. Brain, 1912, 34, 296-509.
  12. von Monakow C. Der rote Kern, die Haube und die Regio hypothalamica bei einigen Säugetieren und beim Menschen. Arb. Hirnanat, Inst. Zurich, 1909, 3, 49—267.
  13. von Economo C J. Zur Physiologie und Anatomie des mittelhirns. Arch. Psychiat. Nervenkr 1910; 46, 275-356;
  14. Schiller F. The Vicissitudes Of The Basal Ganglia (Further Landmarks in Cerebral Nomenclature). Bulletin of the History of Medicine
  15. 1967;41:515-538.
  16. Oppenheim H. Lehrbuch der Nervenkrankheiten. Berlin S. Karger 1894. translated 2nd edn : Textbook of Nervous Disease. New York, G. E. Steckert, 1911.
  17. H. McDowdl and J. M. Cedarbaum, in Clinical Neurology, eds. A. B. Baker and R. J. Joynt (Philadelphia:]. B. Lippincott Company, 1990), pp. 1-97.
  18. Goetz T, Arslan A, Wisden W, Wulff P. GABA(A) receptors: structure and function in the basal ganglia. Prog Brain Res. 2007;160:21-41.
  19. Lanska DJ. Nhe history of movement disorders. Handbook Clinical Neurology. Chapter 33. 2010;95:501-46.


Book Review: One by One by One

Aaron Berkowitz, MD, PhD
María Jimena Alemán

Over this past year, we have all come to wonder what we can do to make a difference in the face of problems that seem so overwhelming. When we think about the scope of the pandemic and other global health issues, the devastating numbers are heart breaking, and it’s easy to lose sight of the individual people and stories behind the statistics. In Aaron Berkowitz’s new book, “One by One by One,” he shares with us the lessons he learned as he tried to make a small difference by helping one individual at a time amid suffering measured in billions.


As a young neurologist, Berkowitz travels with the NGO Partners in Health to Haiti. After the earthquake in 2010, Partners in Health had built the largest solar-powered hospital in a low-income country anywhere in the world as part of their mission to “bring the benefits of modern medical science to those most in need of them and to serve as an antidote to despair.”1

Aspiring to live up to these words, Berkowitz is eager to help his colleagues in Haiti, who inspire him with their incredible devotion to caring for their patients under the most challenging circumstances. Through the book, we learn about the dire consequences of life and medical care in Haiti. Although Berkowitz was one of 100 neurologists at the Brigham and Women’s Hospital in Boston, in Haiti, there was one neurologist for more than 10 million citizens.

There, he meets Janel, a 23-year-old man with the largest brain tumor he had ever seen. Working against impossible odds, Berkowitz tries to save Janel’s life by arranging for him to have brain surgery back in Boston. As new challenges and unexpected events arise, we learn not only about Janel’s journey, but also about Berkowitz’s struggle to find the courage to do what is right despite many adversities.

María Jimena Alemán

María Jimena Alemán

“One by One by One” is a story of juxtapositions. Big problems and bigger ideals. Poverty and abundance. Naivete and hope. Triumphs and failures. Through a humble and honest view of global health inequities, Berkowitz takes us onto the front lines of working in global neurology from the field’s life changing possibilities to its complex challenges. While he provides more questions than answers, his insightful and thought-provoking reflections on ethical dilemmas will widen your view of the world.

This story is set to become a favorite for readers who admire the work of Atul Gawande and Oliver Sacks. Filled with inspiring and humorous passages, it is a book that is as enjoyable as educational.

Written with moving and powerful Haitian Creole proverbs, such as men anpil chay pa lou (many hands make the burden lighter) and tout moun se moun (every person is a person), this story’s teachings will undoubtedly resonate with you long after you’ve put the book down. •

References

Our Mission at PIH®. Partners In Health. (n.d.). https://www.pih.org/our-mission.


María Jimena Alemán is currently a medical student at Universidad Francisco Marroquín in Guatemala. She is interested in global neurology and health equity.

The WFN Inside, Continued: The Constitution & Bylaws Committee and the Neurosonology Specialty Group

Wolfgang Grisold

Wolfgang Grisold

Wolfgang Grisold

In this issue, we will introduce the Constitution & Bylaws Committee, chaired by Anna Hege Aamodt (Norway). This committee ensures that the constitution and bylaws are correct and updated. Conversely, the trustees, often as requested by members, consider to implement changes, which are first scrutinized by this committee for feasibility and practicalities before they are up for voting.

From the WFN Speciality groups, Prof. Kurt Niederkorn will report on the activities of the Neurosonology Specialty Group.

Anne Hege Aamodt is the chief physician at the Headache Clinic and senior consultant at the Stroke Unit at Oslo University Hospital, Norway. She has a broad interest in cerebrovascular and headache research and is the coordinating investigator of several international and national trials. She has organizational leadership, experience in national and international scientific organizations, and was the president of the Norwegian Neurological Association from 2014-2021.

WORLD FEDERATION OF NEUROLOGY, Constitution and Bylaws Committee

Anne Hege Aamodt

Anne Hege Aamodt

The Constitution and By-Laws Committee has members representing all regions. Anne Hege Aamodt is the chair of the committee, representing Europe and Norway. Akram Al-Mahdawi (Iraq) and Hani Aref Pan Arab (Egypt) represent the Pan Arab region, Gagandeep Singh (India) represents Asia-Oceania, Terrence Cascino from USA is represents North America, Fernando Gracia (Panama) represents Latin America, and Thérèse Sonan from Ivory Coast represent Africa.

With the representatives from the different regions, the bylaws committee is well-prepared to work with its main tasks helping the Trustees with the evaluation of proposals for the revision and improvement of the bylaws. The committee aims at providing adaptation and improvement to improve the structure and the function of the Federation. Changes in the bylaws have to be carefully considered by the committee, before voted on by the Council of Delegates after discussion of a resolution presented by the Trustees.

Kurt Niederkorn

Kurt Niederkorn

The other task of the committee is to review and discuss any inquiry into matters pertaining to the organisation and functioning of the Federation, to help the Trustees with decisions in such matters.

The committee has been supporting the president with advice regarding the electronic voting. Electronic voting was planned before the pandemics to aid the number of people involved in making important decisions when it is not possible to meet physically.

Other points were the discussion of changing the Articles of Association to include a role for the immediate past president to ensure continuity and the length of time this would be required for. The conclusion of the committee was that this statutory position is not needed. Furthermore, the appointment of a non-executive trustee to comply with the rules of the charity commission has been discussed, such as including  people from other fields and to increase the breadth of knowledge and opinion. For instance, a lawyer, an economist, or a patient advocate has been discussed. Adding board members puts an additional strain on the WFN finances. However, we recommend that additional board member(s) advisors could be brought in as and when necessary.

For the time being, the committee is working on Standard Operating Procedures that outline areas of responsibly with updated charges, aims, and a protocol.

WFN Neurosonology Specialty Group

For the WFN Specialty groups, Prof. Niederkorn was so kind summarize the impressive activities of the WFN Neurosonology Specialty Group.

Prof. Kurt Niederkorn has been the Chairman of the Neurosonology Specialty Group/WFN since 2019. He has a long experience with neuro ultrasound, and has organized national (Austria) and international courses. He was the secretary of the Neurosonology Research Group/WFN 1993-2001. He works at Graz University, is a professor of Neurology since 1996 and was the vice chair until 2013 of the Dept. of Neurology Graz, Austria. From 2001-2019 he was the head of the Stroke Unit and Stroke Outpatient Service and Neurosonology Lab at the university clinic in Graz

The Specialty Group has a large membership, which can be found on the WCN website.

The Specialty Group was founded in 1977 and endorsed by the WFN in 1981. It is chaired by Kurt Niederkorn and its purpose is the promotion of science and research as well as education and training in the field of ultrasonic techniques (brain vessels and parenchyma and muscle, nerve). This has been a growing and expanding field and modern diagnostics of stroke need ultrasoound equipment. In addition, the group also fosters the development of nerve and muscle ultrasound.

The Specialty Group organizes biannual meetings (2011 Beijing, 2013 Sofia, 2015 Chile, 4/2019 Linz/Austria- Joint meeting with ESNCH, around 300 participants); for 11/2022 a meeting is planned in Korea.

The Specialty Group organizes and co-sponsors international teaching courses and workshops (2014 Lima, 2015 Georgia, 2019 Kazakhstan).

The International Certification in Neurosonology (GM v Reutern/E.Bartels/S Horner, in cooperation with ESNCH) worldwide has been successfully passed by 180 applicants.

Presently, it has 415 members from 50 countries who contribute Euro 25/year for the society. The Specialty Group is constituted from different Chapters: Asia, Latin America, Bulgaria and Georgia.

It has a homepage at https://www.nsrg.net (Content: meetings information and links, guidelines and recommendations). Applications for membership can be made to : alexander.razumovsky@specialtycare.net.

Both the Committees and the Specialty Groups contribute to the vital functions of the WFN.

For each issue of World Neurology, we will continue to introduce a WFN Committee and a Specialty Group. •

Wolfgang Grisold is Secretary-General of the WFN.

Report of Istanbul, Turkey Department Visit

By Dr. Imane Hajjaj

Imane Hajjaj

Imane Hajjaj

I was reading a regular newsletter from World Federation of Neurology, when I saw the announcement of “The Department Visit.” It stated that it was a one-month long visit, which suited me since it wasn’t possible for me to stay away from my country more than this period. Therefore, I decided to participate in and subsequently applied for the Turkey offer.

The choice included fourcities (Istanbul, Konya, Ankara, and Izmir). All of these cities were interesting, although I had a preference for Istanbul. My first objective for applying for this grant was to see how a neurology department looks like outside my country and see the difference concerning organization, systems, and logistics of the care of the neurological patient. Second, I was interested in having an idea about the most frequent diseases and their treatments. I had the answer, and it was a positive one. I booked my flight, and I went to Istanbul. Yes. It was the city I chose. My visit occurred from Dec. 10, 2019, to Jan. 8, 2020.

My accommodations were a 3-minute walk from my hotel to the “Cerrahpaşa Tıp Fakültesi” hospital. On the first day, I met the head of the neurology department, Prof. Sabahattin Saip, who welcomed me and told me that the hospital experienced some damage from a new earthquake, and they were obliged to build a temporary neurology department. Hence, it was a transition period. Then, I met the smiling and nice Prof. Derya Uluduz. With her, I saw for the first time a Doppler embolic shower. On the same first day, I met Prof. Melih Tütüncü and Prof. Aksel Silva. I assisted them at outpatient (poliklinik). It was a rich set of outpatient cases: CADASIL, MS, neurosarcoidosis, Fabry, Behcet, Lyme, spastic paraparésie, among others.

Neurology consultations (polikilinik noroloji) are specialized. There are rooms devoted to MS, dementia, abnormal movements, neuropediatrics, stroke, peripheral nerves, and others. The consultation rooms have computers with intranet and internet, and the neurologists often use them to fill in the patients’ files, do research and see the MRI images.

I spent most of the time of my traineeship between neuropediatric outpatient and EEGs of children. During the child video-EEG lecture, discussions were rewarding and fruitful between neurology residents. Prof. Ahmet Veysi, Demirbilek and us saw many types of seizures (interesting and rich bank of seizure types). Many times before giving the EEG report to a patient, we met the patient’s parents, and we obtained more information about his/her history and evolution under treatment. I noticed that there were many patients under treatment for years even if they were free of seizures. Moreover, Prof. Veysi loved to keep contact with his patients even when they grew up and were more than 16 years old and had to go to adult outpatient. In neuropediatric consultation, more cases were of epilepsy and genetic disorders.

Photo taken on my last day in the neurology department (Istanbul)

Photo taken on my last day in the neurology department (Istanbul). From left to right: Prof. Derya Uluduz (neurologist), Dr. Imane Hajjaj (author, neurologist), Dr. Zeynep Ece Kaya (resident in neurology), and Prof. Sabahattin Saip (head of neurology department).

Other interesting outpatients included multiple sclerosis and other white matter disorders (with Prof. Silva and Prof. Melih). Many cases required reflection and discussion between these two teachers and sometimes the consultations ended around 7 p.m. The choice of MS medications is wide, the switch is often easy, and the MRIs are easy to perform on a regular basis. What I appreciated was the use of the CDs to see the images of the MRI (or on their smartphones). It was exceptional to see a patient bringing pictures with them, and on the other hand, we found with them their files containing their blood tests and medical reports.

I also attended the performance of EMGs with residents and attached neurologists. I appreciated the fact that they give sheets where we explain to patients what an EMG is and how to prepare it.

What drew my attention most was that the patients who brought self-adhesive labels containing their insurance code and their names, and doctors put this label on prescriptions and vouchers for checkups and imagery.

I had the opportunity to visit the neurology department side of the hospital, which was relocated because of the earthquake to the radiology and neurosurgery building. There was one patient per room and was accompanied by a family member. The room was adequately equipped with everything related to a neurological patient.

One of the things that I liked and appreciated was the daily midday meeting. It is a moment of meeting of all the neurological medical team (professors, attached neurologists, residents in neurology) that takes place from 12:30 p.m. to 1:30 p.m., and it is a time to have lunch as well. (It is often offered by the service but the doctors can bring their own lunches with them.) The team meets again to make a presentation, or discuss a clinical case or MRI image. Sometimes the team brings back a patient who describes his/her illness, and the doctors ask him/her questions, try to discuss the case, make the right diagnosis, and offer the adequate therapy.

There is a beautiful atmosphere between residents, teachers, and paramedics. The entire department of neurology celebrated the New Year 2020 with a rich and varied buffet and a large cake. Another day, residents prepared a surprise for their teacher on the occasion of his birthday. Patients offer their doctors gifts to show their recognition and satisfaction. I thought I would have a language problem, but I met professors and residents who speak English or even French and who found it easy to translate and explain the cases of the patients to me.

My last day with the neurology team was focused on an article in English, and the discussion was rich and addressed the social and human side of medical practice.

My stay in Istanbul was an enriching experience for me, and I find that a month is a short period, but it is quite enough to have an idea about the functioning of a neurology service. Many thanks go to all Turkish neurologists I met. Thank you to the Turkish Society of Neurology and to the World Federation of Neurology, and a special thought to Burak Tokdemir and Miray Atacan. •

Dr. Imane Hajjaj is a neurologist in Agadir City, Morocco.

An Epidemic of Mucormycosis Strikes India During the COVID-19 Pandemic

By Chandrashekhar Meshram

Chandrashekhar Meshram

Chandrashekhar Meshram

The second wave of the COVID-19 pandemic was devastating in India with a sudden spurt in cases during the second quarter of the year, and with the count of daily cases crossing 400,000. During this pandemic, there was another epidemic of the fungal infection mucormycosis.

This pandemic and epidemic completely exposed the lacunae in the health care system in the country. There was a shortage of medicines, a shortage of hospital beds, a shortage of oxygen supply, and a shortage of health care personnel, resulting in high morbidity and mortality. According to the statement on June 28 by the Union Health Minister, 40,845 cases of mucormycosis were reported in the country. Out of these, 85% patients had COVID-19, 62% had diabetes as a comorbidity, and 63% of patients had received steroids. The alarming fact is that 32% of the patients were in the age group of 18 to 45 years.

Mucormycosis is caused by saprophytic fungi of the order Mucorales, which are found in decaying organic matter and soil samples. Rhizopus Arrhizus is the most common etiological agent in India. Mucormycosis is an angioinvasive disease causing tissue infarction and necrosis. Rhino-orbito-cerebral mucor is the most common presentation, followed by pulmonary, cutaneous, gastrointestinal, renal, and disseminated disease.

Rhino-orbito-cerebral mucormycosis (ROCM) is often encountered by neurologists. Clinical manifestations of ROCM syndrome include new onset unilateral headache, facial pain, facial numbness, orbital pain, diplopia, ophthalmoplegia, impairment of vision, orbital swelling, ptosis, proptosis, papilledema, nasal discharge, and epistaxis. Black discoloration of skin and mucosa are characteristic of mucor infection. Sometimes there is cavernous sinus thrombosis and internal carotid artery block. The majority of patients with ROCM in association with COVID-19 develop symptoms between day 10 and day 15 post COVID-19. However, delayed presentation can occur up to three months.


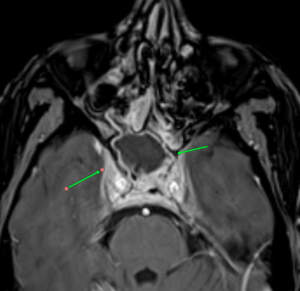
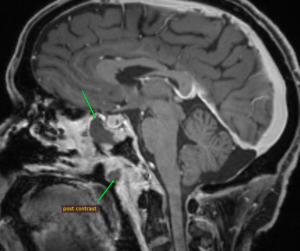
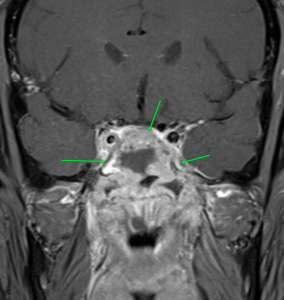
MRI images of mucormycosis with cavernous sinus involvement in a patient with COVID-19.

Imaging findings on CT or MRI that suggest the diagnosis are non-enhancing hypointense mucosa over nasal turbinate and nasal septum (black turbinate sign), concomitant involvement of paranasal sinuses and orbit, bone erosion or destruction, cavernous sinus involvement (figure), and ischemic stroke.

The diagnosis is confirmed by demonstrating fungus with special stains in tissues obtained from nasal scraping or surgery.

Mucormycosis is a medical emergency, and treatment should start with antifungal drugs, surgical intervention, and correction of metabolic abnormalities or risk factors. Amphotericin B is the first-line drug of choice. Liposomal form of Amphotericin B (LAmpB) is preferred in view of a better side effect profile. The efficacy of conventional deoxycholate amphotericin B (dAmpB) is not inferior to the liposomal form but has more side effects. However, the cost of LAmpB is 10 times more. Nephrotoxicity is the most common side effect of dAmpB.

Other drugs used in the treatment are posaconazole and isavuconazole. Oral medication can be used for longer duration. The duration of treatment is not known and has to be decided on a case-to-case basis. Ampho B is recommended for initial 4-6 weeks, which can be followed by posaconazole or isavuconazole for a few more weeks.

Surgical treatment includes debridement or excision of necrotic tissue. Depending on the site of involvement, an ENT surgeon, ophthalmologist, dental surgeon, and neurosurgeon should be part of the team. Surgical intervention at early stage improves the outcome. Functional endoscopic sinus surgery, paranasal sinus debridement, and orbital exenteration are commonly required surgical procedures in ROCM.

The major drawbacks in managing mucormycosis in India are a gap in treatment protocol and non-affordability of LAmpB due to financial constraints.

The mortality rate of mucormycosis in India is in the range of 28–52%, and it increases to 80% in intracranial extension of disease. High mortality is due to delays in seeking medical attention and diagnosing the disease and challenges in managing the advanced stage of infection. There is an urgent need to increase awareness among the general public and doctors for early diagnosis and treatment.

The intriguing question is why there has been such a recent spurt of cases of mucor in India? Though mucormycosis is globally distributed, its estimated prevalence even before the COVID-19 pandemic was 70 times higher in India as compared to global data. The possible reason for the high prevalence is the abundant presence of Mucorales in the community and the hospital environment and the high prevalence of diabetes in the Indian population. The sudden spurt during the second wave might be due to a lowering of immunity by the new strain of COVID-19 making these patients susceptible for fungal infection. •

Chandrashekhar Meshram is chair of the The Tropical and Geographical Neurology Specialty Group of the WFN.

Excitement in the Air

William Carroll, MD

By Prof. William Carroll, WFN President

Despite the dampening effect of the pandemic on all aspects of our lives, the next few months look set to present a welcome diversion. This month, we celebrate the Eighth World Brain Day (WBD), and in October, the XXV World Congress of Neurology (WCN) during which the WFN Council of Delegates will hold its Annual General Meeting and elect the next president, vice president, and trustee.

The first World Brain Day was the idea of Prof. Mohammad Wasay of Pakistan and was held in 2014. Since then, the WFN has held consecutive World Brain Days on July 22 to celebrate the foundation of the WFN, to promote awareness of and advocate for better care and treatment of the brain and nervous system. With each World Brain Day, the WFN has made significant advances in the preparation, focus, and delivery of the key messages.

In recent times, the WFN has partnered with a member of the Global Neurology Alliance, extended the campaign from one day to two or three months and engaged in an ever-enlarging media and social media program.

The WBD is our premier annual event. It’s a time of intense collaboration with a member of the GNA whose disease is the subject of the WBD campaign. In successive campaigns, we have seen the numbers of people reached through the promotional activities rise steadily and are now at more than 50 million. At no other time during the year does the WFN have the opportunity to reach so many people and to promote our mission in such a unique way. The opportunity to focus on a single disease or area of neurological health provides unparalleled scope for the WFN and GNA partner to illustrate the value of such global advocacy. It also enables WFN member societies to connect with the WFN over a two- to three-month period in the latter half of each year.

The WFN is indebted to the WBD Committee chaired by Prof. Tissa Wijeratne and to our media partner, Yakkety Yak, headed by Ashley Logan.

This year, we are proud to have the Multiple Sclerosis International Federation as partners in the promotion of the need for effective treatment for MS. There are highly effective treatments available that can dramatically reduce the rate of disability accrual, and in some instances reduce the level of disability, but they are woefully inaccessible to large numbers of people with MS. Indeed, this campaign is as much about informing people of the benefit of highly effective treatments as it is about highlighting the inequities of access to those therapies. Inequity of access to neurological services and to brain health in general is a core focus of the WFN which it, in turn, shares with the WHO.

The WCN is the premier biennial event for the WFN where the educational effort is focused on advancing the knowledge and practice skills of neurologists, particularly young neurologists. The effort that the WFN and Kenes, our PCO, make for the WCN to be presented as one of the pre-eminent educational opportunities is enormous but worth it. This effort, and the recognition of it, depend almost entirely on the Scientific Program Committee and its chair. We are indebted to Prof. Chris Kennard for his outstanding devotion to the 2019 WCN and this upcoming World Congress. He joins a number of other celebrated senior figures who have each built an admirable record for the WCN programs. After the 2021 Congress, Prof. Kennard will step down and his place will be taken by another worthy individual.

The chair of the Scientific Program Committee must have broad neurology experience including at clinical, scientific, and academic levels. The chair must also be aware of the historical development of neurology and its specialties and the evolving trends. It is the crafting of this perspective with the selection of the leading teachers and lecturers that is a skill often not acknowledged by us. The WFN has benefited greatly from the efforts of Prof. Kennard.

A World Congress of Neurology is a unique event. Although large annual neurology congresses, such as the AAN and EAN annual meetings, are held in different locations within North America and Europe and provide the neurological fraternity with essential updates, the WCN has the ability to complement them both by rotating locations around the world. The WCN, located in a different world region and developed over two years by a Scientific Program Committee influenced by that region, attracts neurologists, young neurologists, and training physicians who might otherwise not be exposed to a major neurology meeting. The opportunity for neurologists in that region to meet, mingle, and interact with an international faculty and colleagues is a profoundly important feature of the WCN. The WCN is also where the prestigious medals are awarded; please see box on page 12 for this year’s awardees.

Of course, each World Congress is the product of a team effort. For 2021 first and foremost is the Society of Italian Neurologists (SIN), the host Member Society, who joined with the WFN to form the key WCN committees. Together with the WFN PCO, Kenes, the committees developed the program with valuable contributions from members of the Global Neurology Alliance, WFN regional organizations, and industry. The role of the Society of Italian Neurologists for this World Congress is remarkably different from usual. Instead of welcoming delegates to the Eternal City, the Society of Italian Neurologists has had a different experience due to the current pandemic.

Working with Kenes and the WFN, they have prepared a spectacular entry point for this virtual World Congress of Neurology, no less than the famous Colosseum. The arriving delegates will also be welcomed by music of Ottorino Respighi or Antonio Vivaldi as they select from an average of 33 sessions to attend each day.

The contribution from the Society of Italian Neurologists has been nothing less than outstanding. Every potential difficulty has been solved promptly and amicably, building an expectation of an outstanding virtual World Congress of Neurology. The WFN is deeply appreciative of the efforts of Antonio Federico, Congress president; Gioacchino Tedeschi, SIN president; and Bruno Giometto, Alfredo Berardelli, Gianluigi Mancardi, and Barbara Frati.

The third and final of these three anticipated events is the Annual General Meeting of the WFN Council of Delegates. It will be held Oct. 2, 2021, the day before the World Congress commences. As in 2020, elections will be electronic so that all eligible member societies will have the opportunity to vote at a time of their choosing.

The results will again be announced during the AGM. Voting this year will be particularly important. Member societies will elect a new president from three candidates and new vice president also from three candidates, and for one elected trustee for the Federation. The elected trustee will take up that office from Oct. 3, and the elected president and vice president from Jan. 1, 2022. Member societies will also decide by vote the venue and host society for the World Congress of Neurology 2025. Information concerning the procedures and timetable for these important elections will be communicated directly to each member society and can also be found on the WFN website.

I thank all who have contributed to the preparation of these upcoming events and look forward to seeing as many friends, colleagues, and member societies as possible participate in them, demonstrating to all that together we are stronger than the challenges we face. •


Previous World Brain Day Topics

2014        Brain Health

2015        Epilepsy (ILAE)

2016        Brain Health and Ageing (ADI)

2017        Stroke (WSO)

2018        Clean Air for Brain Health (WFN Environmental Neurology SG)

2019        Migraine (IHS)

2020        Parkinson’s Disease (IPD and MDS)

From the Editors

Steven L. Lewis, MD, Walter Struhal, MD

We would like to welcome all neurologists worldwide to the July-August issue of World Neurology. This issue begins with the important and sobering update by Dr. Chandrashekhar Meshram about the epidemic of rhino-orbito-cerebral mucormycosis occurring within the COVID-19 pandemic, including its current treatment recommendations.

On a more uplifting note, WFN President Prof. William M. Carroll provides us a number of important updates in his President’s Column, including the ongoing festivities for this year’s World Brain Day, the exciting plans for the World Congress of Neurology just a few short months away, and the Annual General Meeting of the Council of Delegates of the WFN.

WFN First Vice President, Prof. Ryuji Kaji also provides an update on the four candidate cities for World Congress of Neurology 2025. This is followed by the statements from each of these candidate cities: Beijing, Brisbane, Istanbul, and Seoul. Following these proposals are the statements from each of the candidates for WFN elected trustee, first vice president, and president.

In this issue’s history column, Prof. Peter Koehler provides a detailed analysis of the likely migraine occurring in the renowned scientist, Christiaan Huygens. And in his ongoing column, WFN Secretary General Prof. Wolfgang Grisold updates us on the activities of the WFN Finance Committee and the Specialty Group on Neuroepidemiology.

Profs. Satish Khadilkar and Sarosh Katrak describe the history and evolution of the highly successful AAN-WFN Continuum Program in Mumbai, and its recent conversion to a digital format. Prof. Mustapha El Alaoui-Faris details his look back on eight years of experience successfully training Sub-Saharan African Neurologists at the WFN Training Center in Rabat, and provides his thoughts for further optimization of these educational efforts. Dr. Lawrence Robbins provides a personal view of setting up a neurology clinic in Central America, and advice for others considering such volunteer opportunities.

Finally, Prof. Aida Kondybayeva updates us on the details of the recent and highly successful neurology Online Update meeting held in Kazakhstan.

Thank you for your interest in World Neurology and the many activities detailed in these issues. We look forward to seeing so many of you attending the upcoming World Congress of Neurology this October. As always, we look forward to your contributions to this publication, including updates on the many recent and ongoing activities of this year’s World Brain Day. •